



Bioidentical hormones are compounds with the same molecular structure as the hormones your body produces. Most come from plant-based sources such as soy or wild yam and are processed to replicate human estrogen, progesterone, and testosterone. They bind to receptors exactly as endogenous hormones do. This structural identity is what distinguishes hormone therapy using these molecules from conventional synthetic HRT.
How do bioidentical hormones differ from conventional HRT?
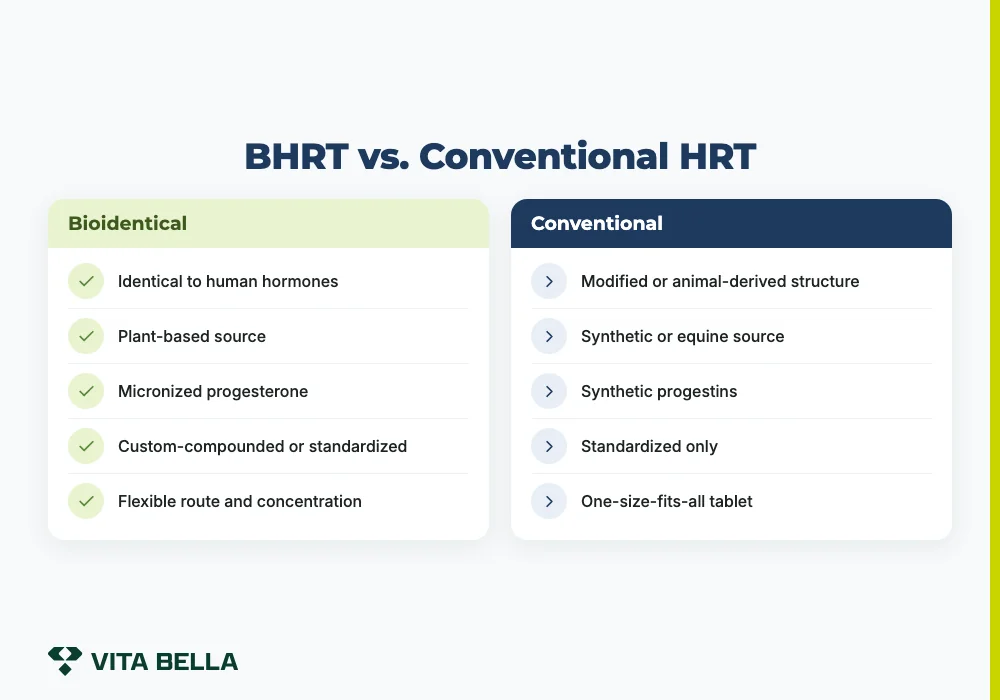
The defining difference is chemical structure. Bioidentical hormones are structurally identical to human hormones. Synthetic counterparts used in traditional HRT are not.
Conventional hormone replacement therapy relies on standardized products, some of which contain animal-derived or chemically modified compounds. Premarin, for example, is extracted from the urine of pregnant mares and contains dozens of conjugated equine estrogens that do not exist in the human body. This is the core of the BHRT vs synthetic HRT debate: molecular fit versus convenience of standardization.
| Bioidentical hormones | Synthetic / conventional HRT | |
|---|---|---|
| Molecular structure | Identical to human hormones | Modified or animal-derived |
| Typical source | Plant-based (soy, wild yam) | Synthetic synthesis or equine |
| Progesterone type | Micronized progesterone | Synthetic progestins (e.g., MPA) |
| Formulation | Custom-compounded or standardized | Standardized only |
| Delivery route | Transdermal, oral, topical | Oral, patch |
Compounded hormone therapy adds another layer of personalization: a licensed compounding pharmacy prepares a formula based on your lab results and a provider's prescription. A 2024 review in Gynecologic and Obstetric Investigation noted that compounded bioidentical formulations allow flexibility in route and concentration that standardized products cannot offer (Santangelo et al., 2024). A licensed provider determines the dose after labs.
Natural hormone therapy using plant-based hormones appeals to patients who want a protocol matched to their individual profile. A one-size-fits-all tablet cannot account for exactly how much estrogen or progesterone your body needs at a given time.
What did the Women's Health Initiative study find about HRT?
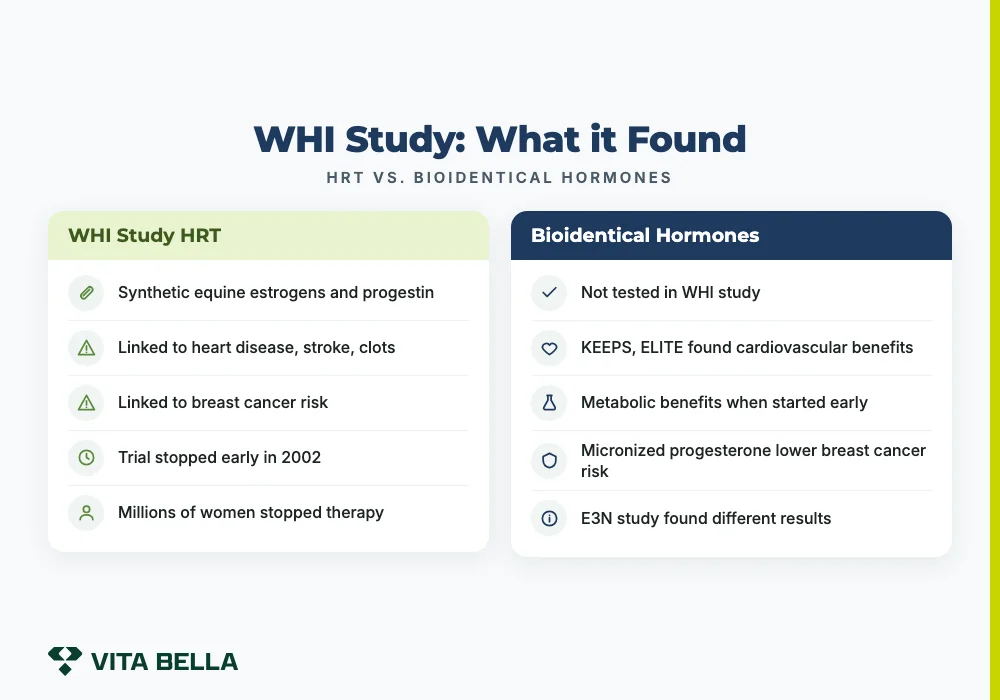
The 2002 Women's Health Initiative study tested synthetic conjugated equine estrogens combined with a synthetic progestin. It did not test bioidentical hormones. The trial was stopped early after linking those compounds to elevated risks of heart disease, stroke, blood clots, and breast cancer.
Media coverage amplified relative risk figures without contextualizing absolute numbers. A "30% increase in risk" corresponded to a small number of additional cases per 10,000 women per year.
Cagnacci and Venier (2019) documented this reporting failure in a history of HRT published in Medicina (Kaunas). Millions of women stopped hormone therapy. The stigma around WHI study HRT outcomes persisted for more than two decades.
The study's limits are the critical point. It used synthetic equine estrogens and medroxyprogesterone acetate. It was never a test of bioidentical estradiol or micronized progesterone.
Newer evidence tells a different story. The KEEPS and ELITE trials found cardiovascular and metabolic benefits when bioidentical estradiol was started close to menopause onset. The E3N cohort study by Fournier et al. (2005) found that micronized progesterone was associated with a lower breast cancer risk than synthetic progestins, a finding the WHI could not capture.
Are bioidentical hormones safer than synthetic hormones?

No hormone therapy is risk-free. Hormone replacement therapy risks depend on formulation type, individual health history, duration of use, and timing relative to menopause.
The evidence supports a more favorable risk profile for bioidentical formulations. A 2022 systematic review and meta-analysis in Menopause examined randomized controlled trials of compounded bioidentical hormone therapy and found adequate safety and symptom-relief efficacy in perimenopausal and postmenopausal women under provider supervision (Liu et al., 2022).
Route of delivery matters alongside molecular type. A 2023 systematic review in Archives of Gynecology and Obstetrics found that transdermal delivery bypasses first-pass liver metabolism and is associated with a lower venous thromboembolism risk than oral routes (Goldštajn et al., 2023). Oral synthetic estrogen and transdermal bioidentical estradiol are not clinically equivalent.
Estrogen progesterone balance is another key variable. Synthetic progestins do not replicate what micronized progesterone does at the receptor level. A 2021 review in Climacteric by Stanczyk et al. noted that the metabolic pathways of bioidentical estradiol and progesterone are better characterized than those of their synthetic counterparts, which supports more predictable clinical management.
In 2021, the National Academies of Sciences, Engineering, and Medicine concluded that compounded bioidentical hormone therapy has supporting evidence for individualized use under provider supervision, while calling for more rigorous trial data (Stuenkel et al., 2021). Long-term use of any hormone therapy warrants ongoing monitoring and regular provider conversations about personal risk factors.
What are the side effects of bioidentical hormone therapy?
Side effects are possible but uncommon at physiological doses. They may include breast tenderness, mild bloating, spotting or irregular bleeding during the early adjustment period, and transient mood shifts as hormone levels stabilize. These effects may occur in the first weeks of therapy and tend to resolve as the provider refines the protocol.
More serious risks apply with long-term use or specific personal risk factors. Venous thromboembolism risk is lower with transdermal delivery than with oral estrogen, per Goldštajn et al. (2023). Patients with hormone-sensitive cancers, active cardiovascular disease, uncontrolled hypertension, or unexplained uterine bleeding require an individual risk assessment before starting any hormone therapy.
Providers monitor hormone levels through labs and quarterly check-ins. If side effects persist, the formulation, dose, or delivery route is adjusted.
Who is a good candidate for BHRT?
Most candidates are women in perimenopause or menopause whose symptoms reduce quality of life: hot flashes, night sweats, poor sleep, mood instability, low libido, or vaginal dryness. Bioidentical hormone replacement therapy is also used by men when declining hormone levels affect energy, body composition, or cognitive function.
A provider evaluates candidacy through symptoms, medical history, family history, and lab results. A comprehensive hormone evaluation before starting treatment establishes a biochemical baseline that guides formulation choices. When lab values read within normal range but symptoms persist, optimal reference ranges often tell a different story than standard ones.
Those who are not appropriate without more extensive evaluation include patients with a history of hormone-sensitive cancers, active cardiovascular disease, unexplained uterine bleeding, or known clotting disorders. Eligibility is determined individually.
People who responded poorly to conventional HRT, or who experienced significant side effects from synthetic progestins, sometimes tolerate bioidentical formulations better. The structural and metabolic differences are a legitimate clinical reason to explore a different approach under provider guidance.
Ready to find out if bioidentical hormones are right for you?
At Vita Bella, a licensed provider reviews your labs and medical history before any protocol begins. Get Started to take the first step toward a hormone plan built around your biology.
Frequently asked questions
Bioidentical hormones share the exact molecular structure of the hormones your body produces; conventional HRT uses synthetic or animal-derived compounds that differ structurally. That difference affects how each type binds to receptors and how the liver metabolizes it.
Research suggests bioidentical estradiol and micronized progesterone carry a more favorable risk profile than synthetic counterparts, particularly for breast cancer and venous clotting outcomes. No hormone therapy is entirely without risk; individual health factors and duration of use both shape the overall picture.
The 2002 WHI study linked synthetic conjugated equine estrogens and a synthetic progestin to elevated risks of heart disease, stroke, and breast cancer, not bioidentical hormones. Later trials using bioidentical formulations showed different and generally more favorable cardiovascular and cancer outcomes.
Possible side effects include breast tenderness, mild bloating, and irregular bleeding during the initial adjustment period; these may occur early in therapy and typically resolve with dosing refinement. More serious risks apply with long-term use and specific health factors, which is why provider monitoring is part of every protocol.
Women with perimenopausal or menopausal symptoms such as hot flashes, sleep disruption, or low libido are typical candidates, and men with declining hormone levels may also benefit. A provider determines eligibility based on labs, medical history, and symptom profile.
Sources
- Liu Y et al. (2022). Safety and efficacy of compounded bioidentical hormone therapy (cBHT) in perimenopausal and postmenopausal women: a systematic review and meta-analysis of randomized controlled trials. Menopause. PubMed
- Goldštajn MŠ et al. (2023). Effects of transdermal versus oral hormone replacement therapy in postmenopause: a systematic review. Archives of gynecology and obstetrics. PubMed
- Santangelo G et al. (2024). Spotlight on Compounded Bioidentical Hormones. Gynecologic and obstetric investigation. PubMed
- Stuenkel CA et al. (2021). Compounded Bioidentical Hormone Therapy: The National Academies Weigh In. JAMA internal medicine. PubMed
- Stanczyk FZ et al. (2021). Bioidentical hormones. Climacteric. PubMed
- Fournier A, Berrino F, Riboli E, Avenel V, Clavel-Chapelon F. (2005). Breast cancer risk in relation to different types of hormone replacement therapy in the E3N-EPIC cohort. International Journal of Cancer.
- Cagnacci A, Venier M. (2019). The controversial history of hormone replacement therapy. Medicina (Kaunas).
















