



Tirzepatide with B6 is a compounded formulation that pairs a dual GLP-1/GIP receptor agonist with pyridoxine (vitamin B6) to support fat loss and reduce gastrointestinal side effects. Vita Bella includes this combination in a licensed provider-guided program where the formulation is determined only after reviewing your labs. The goal is a protocol built around your metabolic baseline, not a one-size default.
What does pyridoxine do in compounded tirzepatide?
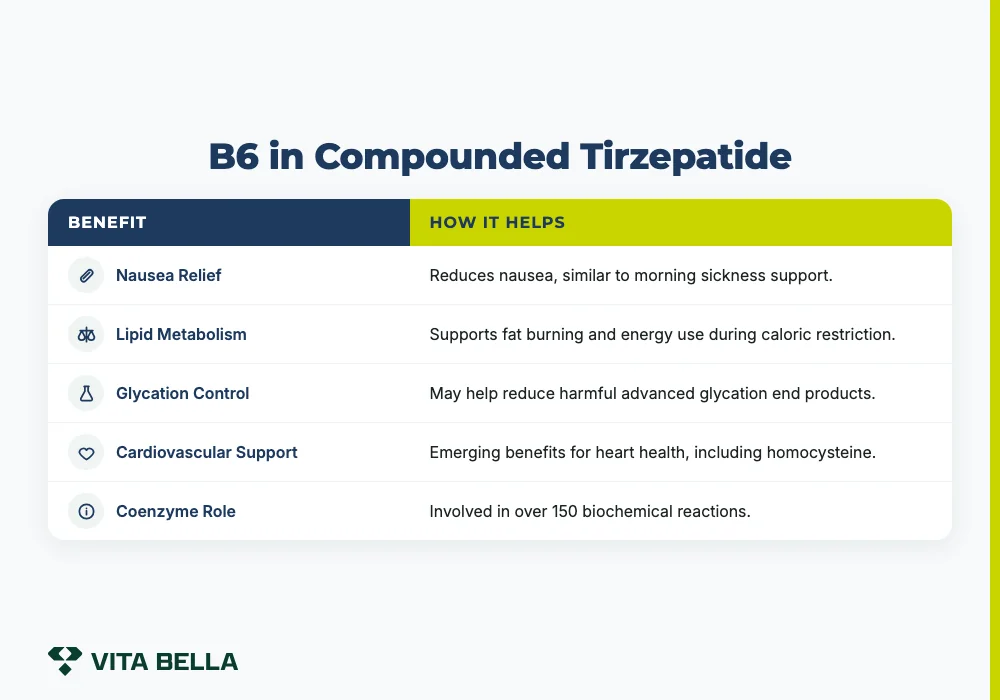
Pyridoxine is the supplemental form of vitamin B6 most commonly used in compounded medications. In compounded tirzepatide ingredients, it fills a specific functional role. According to Stach et al. (2021, Nutrients), vitamin B6 is a coenzyme in more than 150 biochemical reactions, covering amino acid, carbohydrate, and lipid metabolism.
In a tirzepatide protocol, these functions translate to four practical contributions:
Antiemetic support. Pyridoxine has a documented history in reducing nausea, including in pregnancy-related morning sickness. The same pathway applies to GLP-1 nausea relief in patients on tirzepatide.
Lipid metabolism. B6 supports fatty-acid oxidation and lipid transport, helping the body use available energy more efficiently during the caloric restriction tirzepatide induces.
Glycation control. A 2024 review in Vitamins and Hormones found pyridoxine may help counteract advanced glycation end product accumulation, relevant for patients managing metabolic syndrome alongside obesity.
Cardiovascular support. A 2022 narrative review in the European Journal of Nutrition identified emerging cardioprotective mechanisms of vitamin B6, including effects on homocysteine metabolism and oxidative stress.
This profile makes pyridoxine a meaningful addition to the compounded tirzepatide ingredient list, not a filler.
Does vitamin B6 help with tirzepatide nausea?
Yes. Pyridoxine is the primary clinical reason it appears in compounded tirzepatide formulations. Nausea ranks among the most commonly reported tirzepatide side effects in GLP-1 therapy, and it is the leading reason patients reduce or discontinue treatment before reaching therapeutic benefit.
Pyridoxine works through central and peripheral antiemetic pathways. That mechanism is well established. It has been used clinically for nausea across multiple medical contexts for decades, and it transfers directly to GLP-1 nausea relief.
The practical benefit is adherence. Patients who manage nausea effectively miss fewer doses. Fewer missed doses means more consistent exposure to tirzepatide's fat-loss effects. Pyridoxine tirzepatide nausea management is not dramatic as a standalone intervention, but its effect on treatment continuity over months is real.
If nausea persists, a provider will examine titration pace, meal composition, and other contributing factors. Pyridoxine is one clinical tool, not the complete answer.
What are the benefits of combining tirzepatide and pyridoxine?
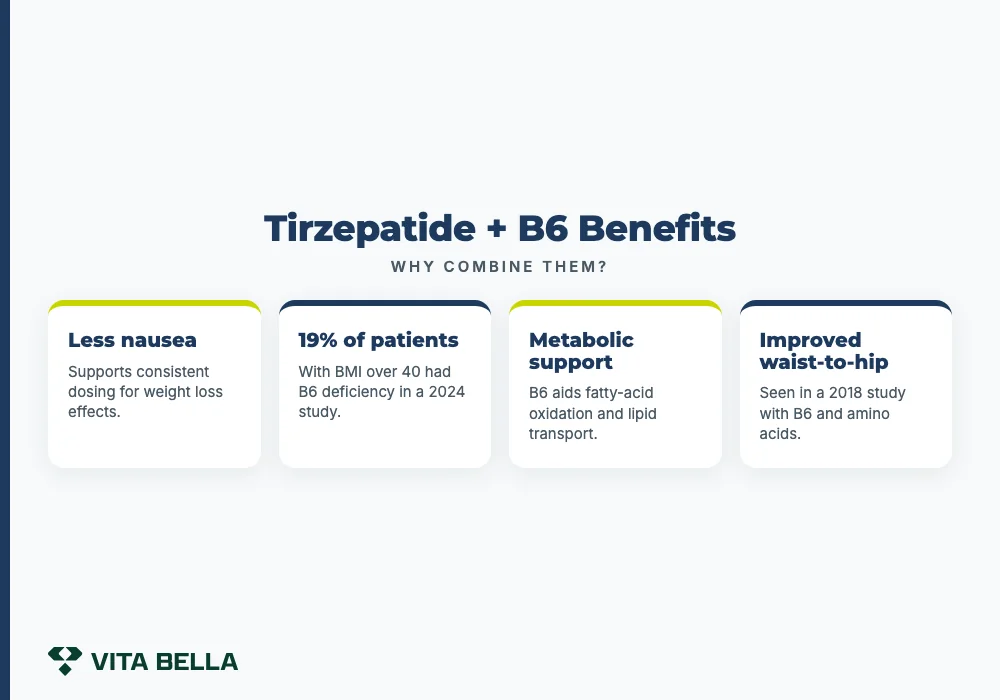
The case for tirzepatide with B6 rests on three distinct contributions.
Tolerability is the most immediate. Less nausea means more consistent dosing and a higher probability of reaching the range where tirzepatide produces its strongest weight loss effects.
Deficiency correction is often overlooked. A 2024 study in the Annals of Family Medicine found that approximately 19% of participants with a BMI above 40 had vitamin B6 deficiency. The population most likely to start tirzepatide frequently arrives with low B6 status. Correcting that deficiency removes a metabolic limiting factor before it slows results.
Metabolic support rounds out the picture. Vitamin B6 weight loss research shows modest but consistent benefits through its role in fatty-acid oxidation and lipid transport. A 2018 randomized trial in the International Journal for Vitamin and Nutrition Research found that combining B6 with branched-chain amino acids in overweight women improved waist-to-hip ratio and lean leg mass over four weeks, though total weight differences were modest. B6-rich foods include chickpeas (1.1 mg per cup) and tuna (0.9 mg per 3-ounce serving). Patients eating these regularly are less likely to be deficient. Those on a reduced-calorie diet without adequate B6-containing foods may need supplementation as part of a monitored protocol.
Lean mass protection during GLP-1 therapy is a related concern. Reading about lean mass considerations during GLP-1 treatment gives fuller context on what a tirzepatide protocol should account for beyond weight on the scale.
Is tirzepatide with B6 more effective than tirzepatide alone?
Tirzepatide with B6 does not produce stronger pharmacological fat loss than tirzepatide alone. Pyridoxine does not increase appetite suppression or alter insulin signaling. What it addresses is tolerability, deficiency correction, and adherence, each of which affects outcomes across a long treatment course.
Tirzepatide alone is highly effective. A 72-week clinical trial published in The New England Journal of Medicine found that non-diabetic participants lost between 15.0% and 20.9% of body weight, with greater reductions in higher dose groups. A 2025 systematic review and meta-analysis in Frontiers in Endocrinology reported mean weight loss of up to 10.7 kg versus placebo across included studies.
No head-to-head trial directly compares tirzepatide alone against tirzepatide with B6 on weight outcomes. What the evidence supports is that B6 deficiency is common in this population, correcting it carries metabolic benefits, and reducing tirzepatide side effects nausea improves adherence. These are indirect but real contributors to total results over months of treatment.
Who is most likely to benefit from added pyridoxine?
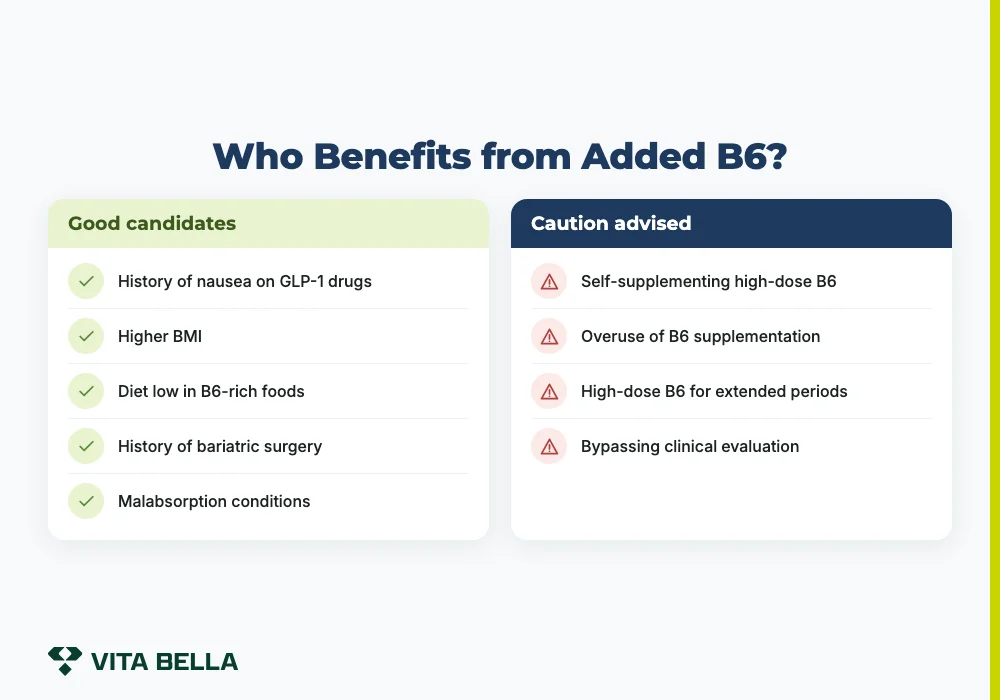
Not every patient needs B6 in their tirzepatide protocol. Your provider decides based on clinical findings. The groups most likely to benefit include:
Patients with a history of nausea on GLP-1 or similar medications
Patients with higher BMI, where B6 deficiency is statistically more prevalent
Patients with dietary patterns low in B6-rich foods such as chickpeas, tuna, salmon, and poultry
Patients with a history of bariatric surgery or malabsorption conditions
One caution matters here. A 2022 study in Nutrition documented a problematic rise in B6 supplementation overuse, particularly in post-bariatric patients. High-dose B6 over extended periods carries a peripheral neuropathy risk, confirmed in a 2023 systematic review in Nutrients by Muhamad et al.
Self-supplementing with high-dose B6 to manage GLP-1 nausea bypasses the clinical evaluation that establishes whether it is appropriate. Provider oversight is not optional in this context.
What your provider evaluates before prescribing
The path to a tirzepatide with B6 protocol starts with labs. A provider reviews what your metabolic baseline shows before you start, selecting a formulation based on your clinical picture rather than a template.
At the evaluation stage, a clinician examines markers related to nutrient status, metabolic function, and contraindications. If B6 deficiency is indicated, including it in the compounded tirzepatide prescription is a straightforward clinical decision. If B6 status is adequate, the provider still determines whether pyridoxine adds tolerability value for that specific patient.
Providers also track how body fat and lean mass change throughout treatment, looking at more than what the scale shows. A complete weight loss evaluation accounts for both fat reduction and lean mass retention from the start.
Compounded tirzepatide prescribed by a licensed provider and prepared by a licensed compounding pharmacy pursuant to a valid prescription is distinct from unmonitored alternatives. Provider oversight determines whether the formulation is safe and correctly matched to your clinical needs.
Start with a provider-guided evaluation
If you are considering tirzepatide as part of a supervised weight management program, the process starts with labs and a 45-minute consultation. Your formulation, including whether a tirzepatide pyridoxine combination fits your profile, is decided by a licensed clinician after reviewing your results. Get Started
FAQ
Does vitamin B6 help with tirzepatide nausea?
Yes. Pyridoxine has recognized antiemetic properties, which is why it appears in some compounded tirzepatide formulations. It may reduce the severity and frequency of nausea, helping patients stay on their prescribed schedule without interruptions.
What does pyridoxine do in compounded tirzepatide?
Pyridoxine is a coenzyme involved in amino acid, carbohydrate, and lipid metabolism, and it has antiemetic effects. In compounded tirzepatide, it is added to improve tolerability and support metabolic function during treatment.
Can B6 boost weight loss results on tirzepatide?
B6 does not amplify tirzepatide's pharmacological action on appetite or insulin signaling. It contributes by reducing nausea, supporting adherence, and correcting B6 deficiency, each of which can influence total outcomes over a multi-month treatment course.
Is high-dose vitamin B6 supplementation safe to take alongside tirzepatide?
High-dose B6 supplementation over time carries a peripheral neuropathy risk. A licensed provider determines whether and how to include pyridoxine in a protocol based on your labs and clinical history, not a self-directed supplement decision.
Do I need a prescription for tirzepatide with B6?
Yes. Compounded tirzepatide with pyridoxine requires a prescription from a licensed provider. It is prepared by a licensed compounding pharmacy pursuant to a valid prescription and is not available without provider review.
Sources
Tian Q et al. (2025). Efficacy and safety of tirzepatide for weight loss in patients with obesity or type 2 diabetes: a systematic review and meta-analysis. Frontiers in Endocrinology. PubMed
Stach K et al. (2021). Vitamin B6 in health and disease. Nutrients. PubMed
Jastreboff AM et al. (2022). Tirzepatide once weekly for the treatment of obesity. The New England Journal of Medicine. PubMed
Wallace R et al. (2024). Hidden hunger: the surprising prevalence of vitamin B6 deficiency in obese patients. Annals of Family Medicine. PubMed
Shakibay Novin Z et al. (2018). The weight-loss effects of branched-chain amino acids and vitamin B6: a randomized controlled trial on obese and overweight women. International Journal for Vitamin and Nutrition Research. PubMed
Muhamad R et al. (2023). The role of vitamin B6 in peripheral neuropathy: a systematic review. Nutrients. PubMed
Vernì F (2024). Vitamin B6 and diabetes and its role in counteracting advanced glycation end products. Vitamins and Hormones. PubMed
Kumrungsee T et al. (2022). Emerging cardioprotective mechanisms of vitamin B6: a narrative review. European Journal of Nutrition. PubMed
Bossard V et al. (2022). Problematic rise of vitamin B6 supplementation overuse and potential risk to bariatric surgery patients. Nutrition. PubMed
For educational purposes only. Not a substitute for medical advice, diagnosis, or treatment. Consult a licensed healthcare provider before making any changes. A licensed provider will determine if a prescription is appropriate after evaluation. Individual results vary. Compounded medications are not FDA-approved for safety, efficacy, or quality.


















