



Enclomiphene benefits men with secondary hypogonadism by stimulating the body's own testosterone production rather than delivering it externally. As a selective estrogen receptor modulator (SERM), it blocks estrogen's negative feedback at the hypothalamus and pituitary, prompting LH and FSH to rise and the testes to respond naturally. For men considering hormone therapy who also want to preserve sperm health, this mechanism is the defining clinical advantage over TRT. A 2014 phase II randomized trial by Wiehle et al. in Fertility and Sterility confirmed that enclomiphene raised testosterone while semen counts remained stable throughout treatment.
How enclomiphene works
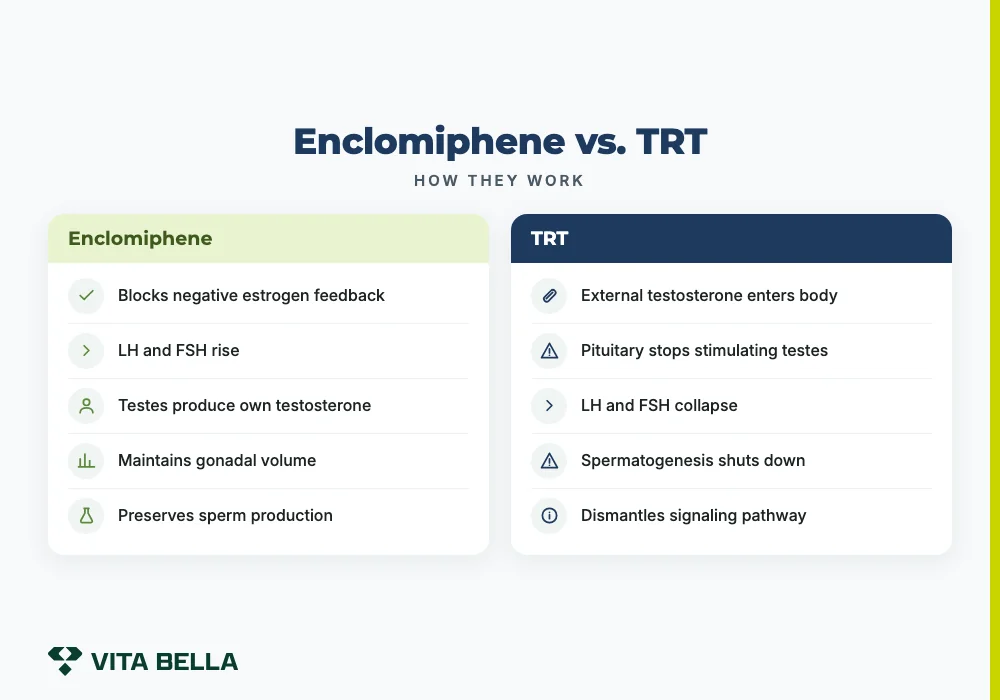
Testosterone production depends on a hormonal feedback loop. The hypothalamus releases GnRH, which signals the pituitary to secrete LH and FSH. LH drives testosterone synthesis in the testes; FSH sustains sperm production. When estrogen rises, it feeds back negatively on this pathway, suppressing both signals and lowering testosterone output.
Enclomiphene is the trans-isomer of clomiphene citrate. It binds estrogen receptors at the hypothalamus and pituitary and blocks that negative feedback. LH and FSH rise. The testes receive a corrected signal and produce more testosterone on their own. No external hormone enters the body.
That is the core difference from TRT. Exogenous testosterone tells the pituitary to stop stimulating the testes. LH and FSH collapse. Spermatogenesis shuts down. Enclomiphene corrects a deficiency in the signaling pathway without dismantling it.
Beyond the core testosterone increase, the enclomiphene benefits that emerge from this corrected signaling loop include maintained gonadal volume, preserved FSH output, and a hormonal profile that resembles a normally functioning HPG axis rather than an externally supplemented one. Secondary hypogonadism is a signaling disorder, not a structural failure of the testes. Treating it by correcting the signal preserves the entire downstream architecture, which matters both for fertility and for the body's long-term regulatory capacity.
Enclomiphene benefits at a glance
| Benefit | Evidence summary |
|---|---|
| Testosterone levels | Significant increase within 2 to 4 weeks (Wiehle et al., 2014; Kaminetsky et al., 2017) |
| Sperm parameters | Stable or improved; spermatogenesis preserved throughout treatment |
| Estradiol effect | Decreased with enclomiphene vs. markedly increased with clomiphene (Saffati et al., 2024) |
| Hematocrit risk | Lower than testosterone gel in pooled trial data (Pastuszak et al., 2015) |
| Adverse event rate | 3.45% for enclomiphene vs. 18.18% for clomiphene in head-to-head cohort data |
| Administration | Oral; a licensed provider determines the dose after reviewing labs |
These enclomiphene benefits are grounded in the same mechanism and have been documented across multiple trial designs. Understanding how each outcome connects to the upstream signaling correction explains why enclomiphene performs differently from both TRT and clomiphene.
Does enclomiphene increase testosterone?
Yes, and the response is consistent across multiple trial designs. Enclomiphene testosterone levels rise because the drug corrects the upstream signaling deficiency rather than adding hormone from outside.
In a phase II randomized controlled trial published in the Journal of Sexual Medicine, Kaminetsky et al. (2017) showed that oral enclomiphene stimulated endogenous testosterone production and sperm counts in men with low testosterone. An earlier phase II trial by Wiehle et al. (2014) in Fertility and Sterility confirmed that most participants reached normal testosterone ranges within two to three months. LH and FSH typically respond within the first two to four weeks. For men evaluating low testosterone treatment options that preserve the natural hormonal axis, this timeline is comparable to TRT on total testosterone outcomes while avoiding HPG axis suppression.
A 2025 systematic review and meta-analysis by Hohl et al. in Archives of Endocrinology and Metabolism pooled randomized controlled trial data comparing enclomiphene and clomiphene against TRT. The analysis confirmed that enclomiphene raised serum testosterone effectively across the reviewed trials. Clinicians evaluating enclomiphene benefits for their patients can draw on this pooled evidence base to contextualize individual lab trajectories against trial-level outcomes.
One measurement that often gets overlooked is free testosterone. Enclomiphene preserves LH and FSH signaling, which affects how testosterone binds to sex hormone-binding globulin in the bloodstream. Why free testosterone matters alongside total is a clinical question providers assess at baseline and throughout treatment, since total testosterone can read as normal while free testosterone remains suppressed. Tracking both values is part of how providers verify the full scope of enclomiphene benefits across the hormonal axis, a man whose total testosterone normalizes but whose free testosterone remains low may need an evaluation of SHBG levels before concluding that the treatment response is complete.
Most men starting treatment notice the core enclomiphene benefits on energy, mood, and body composition emerging around the two to three month mark. Testosterone levels tend to stabilize by six months, based on clinical monitoring data reviewed by Rodriguez et al. (2016) in Expert Opinion on Pharmacotherapy.
Does enclomiphene preserve fertility?
Yes. This is the most clinically significant enclomiphene benefit for men in their reproductive years, and the sharpest point of differentiation from standard low testosterone treatment with TRT.
FSH drives spermatogenesis. TRT suppresses FSH because exogenous testosterone tells the pituitary that production signals are no longer needed. Most men on TRT see sperm counts fall to near zero within months. The recovery period after stopping can be unpredictable and lengthy. For men planning to have children, understanding which enclomiphene benefits apply to their situation, specifically the preservation of FSH-driven sperm production, is often the deciding factor in choosing it over TRT. A man who starts TRT and later wants to conceive faces a window of hormonal uncertainty that may require months of waiting; a man who starts enclomiphene faces no such interruption.
Enclomiphene inverts this outcome. In the Wiehle et al. (2014) phase II trial, semen counts remained stable throughout the entire treatment period despite significant testosterone increases. That finding directly challenged the assumption that treating low testosterone requires accepting fertility loss as a trade-off. A retrospective comparative study of 66 men by Saffati et al. (2024) in Translational Andrology and Urology reinforced this, documenting preserved sperm parameters and gonadotropin levels over the follow-up period for men treated with enclomiphene.
For men already on TRT, sperm outcomes when switching from TRT involve a recovery phase because HPG axis suppression takes time to lift after stopping. Enclomiphene avoids that suppression entirely. For men who have not yet started TRT, enclomiphene for fertility means keeping reproductive options open without ever requiring an interruption or recovery period.
The enclomiphene benefits here are not incidental. Preserving FSH is a direct and predictable consequence of how the drug interacts with the pituitary signaling loop. That option stays open throughout treatment.
How does enclomiphene compare to TRT?
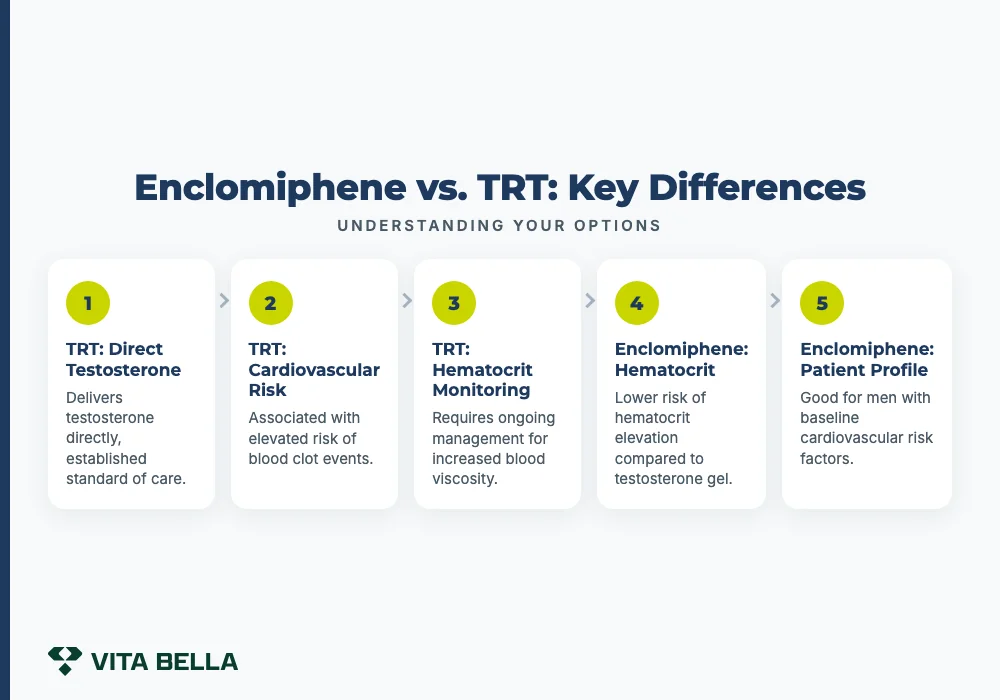
Both options raise testosterone effectively. The mechanisms, trade-offs, and patient profiles where each option fits differ in ways that matter for long-term outcomes.
TRT delivers testosterone directly through injections, gels, patches, or pellets. It is effective and has decades of evidence. The Endocrine Society's 2018 clinical practice guideline by Bhasin et al. in JCEM established TRT as the standard of care for men with confirmed hypogonadism, with the strongest indication in primary hypogonadism where the testes cannot produce testosterone regardless of signaling.
The cardiovascular risk profile of TRT is a separate and significant consideration. A 2024 systematic review and meta-analysis by Cannarella et al. in Asian Journal of Andrology found that TRT is associated with elevated risk of vascular thromboembolic events. A 2024 review by Corona et al. in Expert Opinion on Drug Safety confirmed that cardiovascular monitoring remains essential for men on long-term TRT, particularly around hematocrit. Elevated hematocrit, a known and dose-related TRT effect, increases blood viscosity and clotting risk. This requires ongoing management, not a one-time check.
On hematocrit specifically, enclomiphene vs TRT comparisons favor enclomiphene. Pooled trial data from Pastuszak et al. (2015) showed that enclomiphene achieved comparable testosterone outcomes with a lower risk of hematocrit elevation than testosterone gel.
For men with borderline hematocrit at baseline or underlying cardiovascular risk factors, this is a meaningful clinical difference. In practice, this means a provider can support testosterone optimization without adding a monitoring burden that requires therapeutic phlebotomy. Erythrocytosis, the pathological elevation of red blood cell mass driven by supraphysiological testosterone exposure, is one of the most common reasons men on TRT need dose reductions or treatment interruptions. Enclomiphene's stimulatory mechanism keeps testosterone within a more physiological range, which explains why hematocrit outcomes differ from those seen with injectable or gel formulations.
HPG axis suppression is the other major divergence. TRT shuts down LH and FSH. Testicular volume typically decreases over time, and natural sperm production stops in most men. Managing HPG axis recovery after stopping TRT is unpredictable and can take months to years.
Enclomiphene works by stimulating the axis, not suppressing it. Discontinuing it simply removes the stimulus, and the system returns toward baseline without the recovery burden that follows TRT.
The candidacy question comes down to hypogonadism type. Men with secondary hypogonadism, where the signaling pathway has failed but the testes remain functional, are the intended population for enclomiphene. A baseline panel with LH and FSH distinguishes secondary from primary hypogonadism before treatment begins. What enclomiphene results look like over time depends entirely on that distinction, since men with primary hypogonadism are unlikely to respond to upstream signaling corrections.
Enclomiphene vs clomiphene
Clomiphene is a racemic mixture: half enclomiphene (trans-isomer), half zuclomiphene (cis-isomer). Enclomiphene is the active component that blocks estrogen receptors and raises LH and FSH. Zuclomiphene has estrogenic activity and a half-life that can extend to several weeks, meaning it accumulates during a treatment course.
That accumulation drives the side effect burden associated with clomiphene. Zuclomiphene acts like estrogen at certain tissues, producing mood disturbances, fatigue, gynecomastia, and reduced libido in a significant proportion of treated men. Over a treatment course, estradiol typically rises rather than falls.
The Saffati et al. (2024) comparative cohort study quantified this directly. Men treated with enclomiphene had an estradiol change of minus 5.92 pg/mL. Men treated with clomiphene had a change of plus 17.50 pg/mL, a statistically significant difference (P = 0.001).
The adverse event rate was 3.45% for enclomiphene vs. 18.18% for clomiphene, with an odds ratio for adverse events of 0.18 (95% CI: 0.07 to 0.44). Those numbers are not close.
Zuclomiphene distributes to fatty tissue and has been detected in serum up to a month after the last dose. In men taking clomiphene for several weeks, this accumulation means estrogenic activity persists long after dosing stops. The practical consequence is that men experience side effects extending beyond the active treatment window, complicating the interpretation of any post-treatment symptom assessment. Enclomiphene clears more predictably, which gives providers cleaner on-treatment data and a more interpretable baseline when labs are drawn after a treatment pause.
The enclomiphene benefits compared to clomiphene are not a marginal safety improvement. It is the same testosterone-raising mechanism with the estrogenic burden removed. Men who tried clomiphene and experienced mood changes, fatigue, or libido problems often do better on enclomiphene because the problem compound is no longer part of the treatment.
Does enclomiphene boost libido?

For men whose reduced sexual desire is linked to low testosterone, yes. Low testosterone is a recognized and reversible biochemical driver of diminished libido. When enclomiphene raises testosterone back toward normal, it addresses that driver directly.
The clinical data supports this. In the Saffati et al. (2024) comparative cohort, decreased libido appeared as a documented adverse event far more often in the clomiphene group than in the enclomiphene group, reflecting enclomiphene's more favorable testosterone-to-estradiol ratio. The phase II trial data from Wiehle et al. (2014) also captured quality-of-life improvements that include sexual interest and function as endpoints.
Timing follows a predictable pattern. Most men notice improvements in libido starting around two to three months into treatment, aligned with when testosterone levels reach a new stable baseline. Energy and mood typically improve on the same schedule. These enclomiphene benefits often arrive together.
Libido is not driven by testosterone alone. Sleep quality, stress, certain medications, and relationship context all contribute. Enclomiphene addresses the hormonal piece. When low testosterone is the primary driver, the response is typically clear and noticeable. When other factors are dominant, correcting testosterone helps but does not address everything by itself.
Enclomiphene benefits on mood and cognitive function
Testosterone is active in the central nervous system as well as peripheral tissues. Androgen receptors are present in areas of the brain associated with motivation, mood regulation, and working memory. Men with low testosterone frequently report cognitive fog, reduced drive, and low mood alongside the physical symptoms. The cognitive and motivational enclomiphene benefits in this category commonly emerge on the same timeline as the libido response, within two to three months as testosterone reaches a new stable baseline.
Enclomiphene benefits for body composition
Testosterone plays a well-documented role in body composition. Low testosterone is associated with increased visceral fat accumulation and reduced lean muscle mass, even when caloric intake is comparable to that of eugonadal men. The enclomiphene benefits on body composition follow from the same HPG axis correction that drives the mood and libido response: as testosterone normalizes, androgen signaling at muscle tissue promotes more efficient protein synthesis and lean mass maintenance.
Men in published clinical cohorts frequently report improvements in fat distribution and physical strength on a timeline consistent with the hormonal response, approximately two to three months into treatment. These changes are incremental rather than dramatic in the short term but accumulate measurably over six to twelve months of sustained testosterone normalization. They are most evident in men who are physically active and have noticed declining exercise performance alongside other symptoms of low testosterone. Correcting the hormonal deficit allows these men to respond more fully to training and recovery than was possible in a hypogonadal state.
Can enclomiphene cause high blood pressure?
Available clinical data do not show enclomiphene causing significant blood pressure elevation. This is relevant because one established concern with long-term TRT is its cardiovascular footprint, and men weighing enclomiphene side effects often ask how the risk profiles compare.
On hematocrit, the most directly monitored cardiovascular marker during hormonal treatment, enclomiphene compares favorably to TRT. Pooled data from Pastuszak et al. (2015) showed enclomiphene raised testosterone with a lower risk of hematocrit elevation than testosterone gel. Elevated hematocrit increases blood viscosity, which is one pathway through which TRT can indirectly raise cardiovascular risk.
Cannarella et al. (2024) confirmed in their systematic review that TRT carries elevated thromboembolic risk. Enclomiphene avoids the hematocrit-raising effect that makes this a concern with TRT.
Enclomiphene side effects men typically report in published cohort data are mild and infrequent. The Saffati et al. (2024) study documented a 3.45% adverse event rate for enclomiphene, with events concentrated in the clomiphene group. No large-scale data connect enclomiphene to clinically meaningful blood pressure increases.
Men with significant pre-existing cardiovascular risk factors, or those taking medications that interact with hormonal pathways, still need a thorough baseline evaluation before starting any hormonal treatment. A licensed provider determines the dose after labs, reviews cardiovascular history, and monitors relevant markers at follow-up visits. This is standard practice for any SERM or hormonal protocol.
Blood pressure specifically has not emerged as a consistent signal in published enclomiphene trials. Whereas exogenous testosterone can influence fluid retention, red blood cell mass, and sympathetic tone, all pathways through which blood pressure may increase, enclomiphene's stimulatory mechanism does not appear to drive these changes to a clinically significant degree. Available cohort data suggest a more favorable cardiovascular risk profile for enclomiphene compared to TRT in the typical secondary hypogonadism patient.
What to expect during treatment
The enclomiphene benefits timeline follows a consistent pattern. Hormonal markers, including LH, FSH, and testosterone, typically begin responding within two to four weeks of starting treatment. Noticeable improvements in energy, mood, and libido usually emerge by two to three months. Testosterone levels tend to stabilize around the six-month mark.
Monitoring covers several dimensions. Providers typically track total and free testosterone, LH, FSH, estradiol, hematocrit, and semen parameters at regular intervals. The exact schedule depends on how quickly levels respond and stabilize.
This ongoing assessment allows providers to catch early signs of estradiol elevation, verify the treatment is working, and adjust if needed.
One practical advantage of enclomiphene is oral delivery. Injections require technique and scheduling adherence; daily gels introduce variability in absorption. An oral medication taken consistently removes those friction points without changing the clinical outcomes.
Vita Bella's enclomiphene program pairs each patient with quarterly provider check-ins and labs ordered through Quest Diagnostics. Adjustments are based on what the labs actually show, not on estimates or symptom reports alone.
Not every man is a candidate. The primary contraindication is primary hypogonadism, where the testes themselves are the source of failure. If LH and FSH are already elevated at baseline but testosterone remains low, the testes are receiving the signal and not responding to it. Enclomiphene amplifies a signal the testes cannot use. A baseline hormone panel identifies this before treatment begins.
Start with your hormone numbers
If the enclomiphene benefits described in this article match what you have been experiencing, the next step is a provider-led assessment of your labs. Vita Bella's process starts with hormone testing through Quest Diagnostics, followed by a 45-minute consultation where a licensed provider reviews your results, discusses your goals, and determines whether enclomiphene fits your clinical picture. Every case is reviewed by a real licensed provider, not AI. Medications are dispensed through FDA-inspected U.S. pharmacies and require a valid prescription from your treating provider. The program is structured to follow established clinical protocols: labs first, then an informed consultation, then a treatment decision, not the other way around.
Frequently asked questions
Enclomiphene is effective for secondary hypogonadism, where the testes are functional but the signaling pathway is disrupted. Multiple randomized trials confirm it raises total and free testosterone to normal ranges within two to three months. It is not effective for primary hypogonadism, where the testes themselves cannot respond to LH stimulation.
Enclomiphene side effects are generally mild and infrequent. A head-to-head cohort study by Saffati et al. (2024) found an adverse event rate of 3.45% for enclomiphene vs. 18.18% for clomiphene, and TRT carries a more significant cardiovascular risk profile, including elevated hematocrit and thromboembolic risk. Spermatogenesis suppression, a standard TRT side effect, does not occur with enclomiphene.
For preserving sperm production, enclomiphene is the clinically stronger option. It maintains FSH levels, which drive spermatogenesis, while TRT suppresses FSH and typically reduces sperm counts to near zero within months. Men with secondary hypogonadism who want to preserve reproductive options are generally better served by starting with enclomiphene.
Published trial and cohort data support enclomiphene use over months-long treatment periods without significant safety signals. Rodriguez et al. (2016) noted a favorable tolerability profile for secondary hypogonadism management. Long-term outcomes beyond current study windows are still being studied, which is why ongoing monitoring with a licensed provider is standard practice.
Enclomiphene is the active testosterone-raising isomer of clomiphene without the estrogenic zuclomiphene component. In the Saffati et al. (2024) comparative cohort, enclomiphene produced a 3.45% adverse event rate vs. 18.18% for clomiphene and a markedly better estradiol profile. Men switching from clomiphene to enclomiphene typically report fewer mood, fatigue, and libido problems.
Sources
- Wiehle RD et al. (2014). Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial. Fertility and Sterility. PubMed
- Kaminetsky J et al. (2017). Oral enclomiphene citrate stimulates the endogenous production of testosterone and sperm counts in men with low testosterone. Journal of Sexual Medicine. PubMed
- Pastuszak AW et al. (2015). Comparison of oral enclomiphene citrate and topical testosterone gels on serum hormones, erythrocytosis, lipids, and PSA. Journal of Sexual Medicine. PubMed
- Saffati G et al. (2024). Safety and efficacy of enclomiphene and clomiphene for hypogonadal men. Translational Andrology and Urology. PubMed
- Hohl A et al. (2025). Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials. Archives of Endocrinology and Metabolism. PubMed
- Cannarella R et al. (2024). Testosterone replacement therapy and vascular thromboembolic events: a systematic review and meta-analysis. Asian Journal of Andrology. PubMed
- Corona G et al. (2024). Cardiovascular safety of testosterone replacement therapy in men: an updated systematic review and meta-analysis. Expert Opinion on Drug Safety. PubMed
- Bhasin S et al. (2018). Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline. The Journal of Clinical Endocrinology and Metabolism. PubMed
- Rodriguez KM et al. (2016). Enclomiphene citrate for the treatment of secondary male hypogonadism. Expert Opinion on Pharmacotherapy. PubMed















