



Male sexual dysfunction covers a group of persistent conditions that prevent men from having satisfying sexual activity, including problems with erections, ejaculation, desire, and orgasm. A large population-based review found that about 31% of men experience at least one form during their lifetime. These conditions rarely resolve without addressing their root cause. Sexual wellness and hormone care is where most effective evaluations begin.
What is male sexual dysfunction?
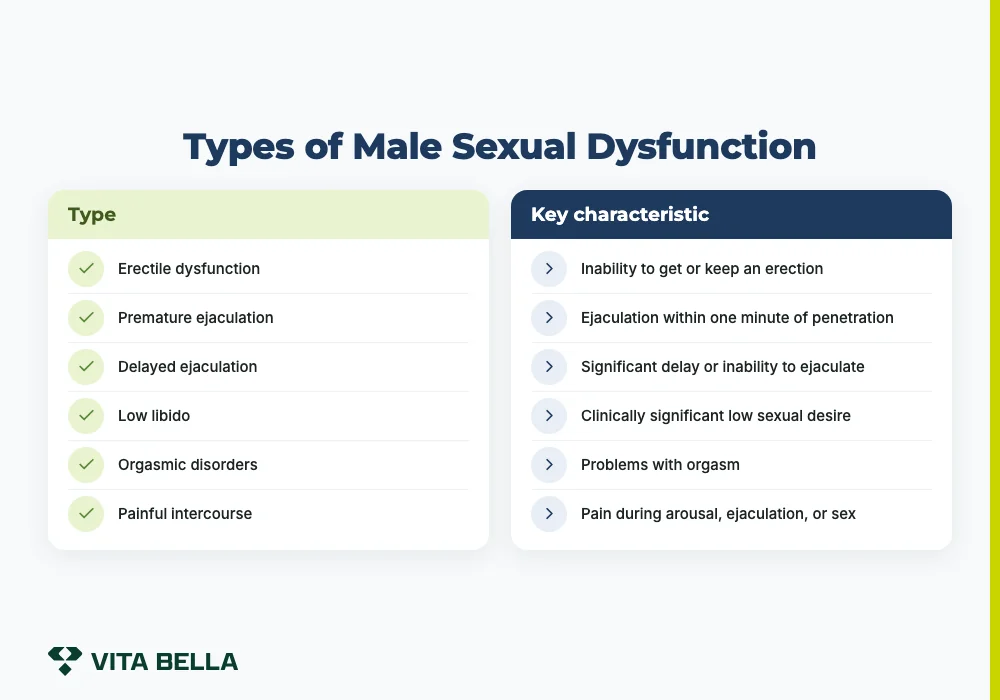
Male sexual dysfunction is any disorder that consistently interferes with a man's ability to engage in or complete satisfying sexual activity. The 2021 European Association of Urology (EAU) Guidelines define it as a spectrum of conditions arising from vascular, hormonal, neurological, and psychological causes, typically acting in combination (Salonia et al., 2021). Most men deal with more than one type simultaneously. That overlap shapes how treatment works.
Main types of male sexual dysfunction
- Erectile dysfunction (ED): persistent inability to achieve or maintain an erection firm enough for intercourse. Research links it strongly to cardiovascular disease, diabetes, and age.
- Premature ejaculation: ejaculation that occurs within approximately one minute of penetration, causing distress. It affects an estimated 20–30% of men worldwide and is one of the most common sexual complaints in clinical practice.
- Delayed ejaculation: a significant delay or inability to ejaculate despite adequate stimulation. Prevalence is approximately 1–4% of men, making it the least common ejaculatory disorder.
- Low libido in men: also called hypoactive sexual desire disorder (HSDD). About 8–10% of men experience clinically significant low sexual desire, with higher rates among older men and those with depression or endocrine disorders.
- Orgasmic disorders: prevalence in community samples ranges from 8% to 19%, increasing with age and comorbid health conditions.
- Painful intercourse: pain during arousal, ejaculation, or sex. Physical and psychological factors both contribute, and it often co-occurs with other conditions described here.
These types frequently overlap. A man experiencing low testosterone symptoms may have both reduced desire and erectile difficulties simultaneously. Addressing the hormonal driver often improves both.
What are signs of sexual dysfunction in men?
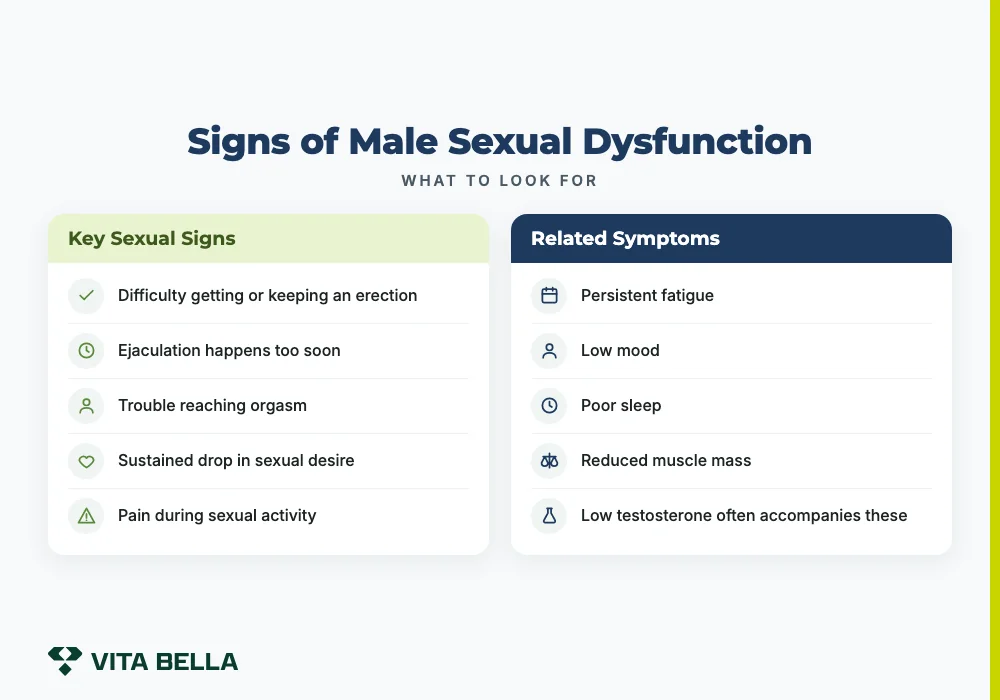
The core signs are consistent changes in sexual function that persist over several weeks. One difficult episode is not a clinical pattern. A recurring problem over weeks or months warrants evaluation.
Key signs include:
- Inability to achieve or maintain an erection during sexual activity.
- Ejaculation that consistently occurs far sooner than desired, causing distress for you or your partner.
- Difficulty or inability to reach orgasm despite adequate stimulation and arousal.
- A noticeable, sustained drop in sexual desire or interest in sex.
- Pain during arousal, ejaculation, or intercourse.
Low testosterone symptoms often accompany and reinforce sexual dysfunction. Persistent fatigue, low mood, poor sleep, and reduced muscle mass frequently appear alongside declining libido and erectile difficulties. When these symptoms cluster together, a lab panel often tells the full story. Providers typically look beyond a single total testosterone number, since binding proteins and other markers shape what that result means. Understanding what a complete hormone assessment actually measures helps men know what to expect before their first provider visit.
Sexual dysfunction also affects mental health and relationships. Left unaddressed, it tends to compound, creating a cycle of anxiety, avoidance, and declining intimacy.
What causes sexual dysfunction in men?
The condition rarely has a single origin. The 2021 EAU Guidelines identify vascular, hormonal, neurological, psychological, and lifestyle factors as the primary contributors, with most cases involving more than one simultaneously (Salonia et al., 2021).
Physical causes
Cardiovascular disease and diabetes are the two most consistent physical drivers. A 2024 systematic review and meta-analysis by Dilixiati et al. confirmed that diabetes significantly raises the risk of erectile dysfunction through vascular damage and impaired nerve function in the penis. Heart disease and obesity restrict blood flow through similar mechanisms.
Hormonal imbalance is a direct driver of these problems. Low testosterone reduces sexual desire and affects the physiological process of erection. Neurological conditions such as Parkinson's disease and multiple sclerosis disrupt the nerve pathways that coordinate arousal and response. Medications, including antidepressants, opioids, and certain blood pressure drugs, can all suppress sexual function as a side effect.
Prostate medications add another layer of risk. A 2016 meta-analysis by Favilla et al. found that combining 5-alpha reductase inhibitors with alpha-blockers for enlarged prostate significantly increased both erectile dysfunction and reduced libido compared to controls.
Psychological causes
Anxiety and stress activate hormonal pathways that suppress libido and interfere with erection. Depression reduces sexual interest and satisfaction. These forces reinforce each other: sexual dysfunction increases psychological distress, which deepens the dysfunction.
Performance anxiety creates a self-perpetuating cycle. One difficult episode generates anticipatory fear. That fear then becomes the obstacle in subsequent encounters.
Relationship conflict and poor communication with a partner make all of these factors worse. The problem almost never exists apart from its relational context.
Lifestyle factors
Smoking constricts blood vessels and reduces penile blood flow. Heavy alcohol use impairs nerve function and hormonal regulation. Physical inactivity weakens cardiovascular fitness, which erectile function directly depends on. Poor sleep raises cortisol and suppresses testosterone production. Both changes degrade sexual health for men over time and are among the most reversible contributing factors.
How is male sexual dysfunction treated?
Effective management follows a clear logic: identify the underlying cause, then apply targeted therapy. Most men benefit from a combination of medical treatment, lifestyle changes, and, where psychological factors are present, supportive counseling.
PDE-5 inhibitors
Phosphodiesterase-5 (PDE-5) inhibitors, including sildenafil and tadalafil, are the established first-line erectile dysfunction treatment. They enhance erection by relaxing smooth muscle and increasing blood flow to the penis. A 2026 systematic review and network meta-analysis by Salonia et al. evaluated on-demand PDE-5 agents across double-blind, randomized, placebo-controlled trials and confirmed clinically meaningful efficacy across patient profiles. A licensed provider determines the appropriate agent and dose after reviewing your health history and labs.
Testosterone replacement therapy
For men with confirmed low testosterone, testosterone replacement therapy addresses the hormonal root of male sexual dysfunction directly. A meta-analysis by Zhu et al. (2020) found that normalizing testosterone significantly improved erectile outcomes in men who had not responded to PDE-5 inhibitors alone. Labs come first. A licensed provider reviews results before determining the appropriate protocol. Men considering TRT who also want to preserve fertility should understand how sperm health is managed during testosterone treatment, since TRT can suppress the body's natural sperm production.
Pelvic floor training and exercise
Exercise has a direct, measurable impact on erectile dysfunction treatment. A 2019 systematic review by Myers et al. found that pelvic floor muscle training significantly improved both erectile dysfunction and premature ejaculation. Regular cardiovascular exercise builds the circulatory capacity that erections depend on and supports natural testosterone production. A diet rich in lean proteins and antioxidants supports vascular function. Quitting smoking and reducing alcohol intake remove direct physiological barriers.
Psychological and relational therapy
Cognitive Behavioral Therapy (CBT), sex therapy, and couples counseling each target the psychological component of male sexual dysfunction. They reduce performance anxiety, shift self-limiting thought patterns, and rebuild intimacy between partners. These approaches work best alongside medical treatment, since male sexual dysfunction rarely has a single cause.
Advanced options
For men who do not respond to medication or conservative measures, clinical escalation is available. Low-intensity shockwave therapy stimulates tissue repair and has shown meaningful results for erectile dysfunction in randomized controlled trials. A meta-analysis by Campbell et al. (2019) confirmed its efficacy. For severe, treatment-resistant erectile dysfunction, penile implants provide a durable resolution. Platelet-rich plasma and other regenerative therapies remain under active clinical investigation.
Is sexual dysfunction in men treatable?
For many men, yes. Significant improvement or full resolution is possible; the outcome depends on the underlying cause and how promptly evaluation happens.
When male sexual dysfunction stems from reversible factors, such as a medication side effect, poor lifestyle habits, or psychological stress, addressing those factors directly often restores full sexual function. Men with chronic conditions like diabetes or cardiovascular disease can achieve meaningful improvement through combined medical management and targeted sexual health therapy, though some ongoing maintenance may be needed.
The 2021 EAU Guidelines confirm that most men with male sexual dysfunction improve with appropriate, cause-directed treatment (Salonia et al., 2021). Early evaluation shortens the path to recovery. Conditions left unaddressed tend to compound over time. The physical and psychological dimensions become harder to separate, and effective treatment takes longer.
When should men see a doctor for sexual problems?
Seek a clinical evaluation when sexual difficulties persist beyond a few weeks, cause personal distress, or appear alongside other symptoms. One isolated episode is not cause for alarm. A consistent pattern is.
Reasons to schedule an evaluation include:
- Erections that are consistently weak or absent.
- Ejaculation that is persistently premature or delayed, causing distress for you or your partner.
- A sustained, noticeable drop in sexual desire.
- Pain during sexual activity.
- Low testosterone symptoms appearing alongside sexual problems: persistent fatigue, mood changes, reduced muscle mass, or disrupted sleep.
Sexual health for men is closely connected to cardiovascular and metabolic health. Erectile dysfunction can be an early marker of underlying heart or vascular disease, which is another reason prompt evaluation matters.
A Vita Bella provider reviews your symptoms, orders relevant labs through Quest Diagnostics, and builds a treatment plan around your specific results. Men's sexual wellness is not a single-variable problem. Effective care addresses both the physical and the hormonal picture. Understanding which values are out of range, and which are technically normal but still suboptimal, makes a significant difference in how the protocol is designed.
Start reclaiming your sexual health
If these patterns sound familiar, a provider-led evaluation is the practical next step. Vita Bella connects men with licensed providers across 47 states for assessments that cover hormones, labs, and men's sexual wellness. Treatment follows your results, not a one-size protocol.
Frequently asked questions
No. Most forms of male sexual dysfunction respond well to treatment. When the underlying cause is identified and addressed, whether hormonal, vascular, psychological, or a combination, the majority of men see significant improvement or full resolution.
Premature ejaculation causes range from neurobiological factors and heightened penile sensitivity to performance anxiety, psychological stress, and relationship tension. Lifelong and acquired forms have different mechanisms, and a licensed provider can help identify which applies and guide the right treatment approach.
Yes. Low testosterone symptoms frequently include reduced libido, weaker erections, and diminished sexual satisfaction. A lab panel confirming low testosterone opens the path to targeted hormone therapy, which typically improves sexual function alongside energy and mood.
Yes. A 2019 systematic review found that pelvic floor muscle training significantly improved both erectile dysfunction and premature ejaculation. Regular cardiovascular exercise also supports the blood flow and hormonal balance that healthy sexual function depends on.
Sources
- Rosen RC. (2000). Prevalence and risk factors of sexual dysfunction in men and women. Current Psychiatry Reports. PubMed
- Salonia A et al. (2021). European Association of Urology Guidelines on Sexual and Reproductive Health, 2021 Update: Male Sexual Dysfunction. European Urology. PubMed
- Salonia A et al. (2026). A comparative evaluation of on-demand phosphodiesterase-5 inhibitor efficacy in erectile dysfunction treatment: a systematic review and network meta-analysis. The Journal of Sexual Medicine. PubMed
- Dilixiati D et al. (2024). Risk factors for erectile dysfunction in diabetes mellitus: a systematic review and meta-analysis. Frontiers in Endocrinology. PubMed
- Myers C et al. (2019). Pelvic floor muscle training improves erectile dysfunction and premature ejaculation: a systematic review. Physiotherapy. PubMed
- Favilla V et al. (2016). Impact of combination therapy 5-alpha reductase inhibitors plus alpha-blockers on erectile dysfunction and decrease of libido in patients with LUTS/BPH. The Aging Male. PubMed
- Carson C, Gunn K. (2006). Premature ejaculation: definition and prevalence. International Journal of Impotence Research. Source
- Chen J. (2016). The pathophysiology of delayed ejaculation. Translational Andrology and Urology. PubMed
- Mark K et al. (2014). The object of sexual desire: examining the "what" in "what do you desire?" Journal of Sexual Medicine. Source
- Zhu J et al. (2020). Testosterone supplements and PDE-5 inhibitor response in men with erectile dysfunction and hypogonadism: a systematic review and meta-analysis. Translational Andrology and Urology. PubMed
- Campbell JD et al. (2019). Meta-analysis of randomized controlled trials on low-intensity shockwave therapy for erectile dysfunction. Therapeutic Advances in Urology. Source
- Delcea C, Popescu A. (2019). International Journal of Advanced Studies in Sexology. DOI
















