



Undiagnosed hypothyroidism means the thyroid gland is making too little hormone and nobody has recognized it yet. It is common. Large studies estimate that about 4% to 7% of people in community-based populations in the USA and Europe have undiagnosed hypothyroidism, and roughly four in five of those cases are the milder, subclinical form (Gottwald-Hostalek and Schulte, 2022). The symptoms are nonspecific and overlap with everyday complaints like fatigue, weight gain, and low mood, so they are easy to put down to other causes or to getting older. When those complaints persist without a clear explanation, a provider-led hormone evaluation that can include thyroid testing is a sensible place to start.
How the thyroid regulates your body
The thyroid sits at the front of the neck and produces two hormones: thyroxine (T4) and triiodothyronine (T3). Most of its output is T4, which the liver, kidneys, and other tissues convert into T3, the more active form. Thyroid hormone affects the metabolism and function of many cells and organs, which is why a shortage can show up in so many different ways (Wilson et al., 2021).
Output is controlled by a feedback loop. The hypothalamus signals the pituitary gland, the pituitary releases thyroid-stimulating hormone (TSH), and TSH tells the thyroid how much hormone to make. Thyroid hormone then feeds back to adjust that signal (Wilson et al., 2021). In primary hypothyroidism, the problem sits in the thyroid itself. The gland cannot keep up, and TSH rises. That is why TSH is the first blood test clinicians order when they suspect an underactive thyroid, while free T4 is used to tell the overt form from the subclinical one.
What are the signs of undiagnosed hypothyroidism?
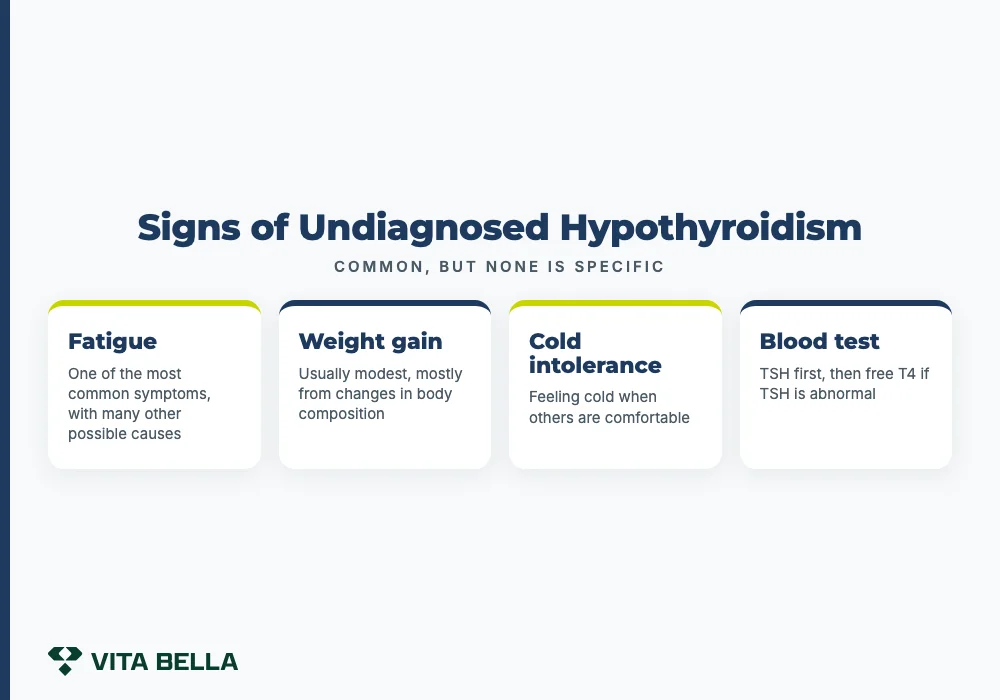
The signs of undiagnosed hypothyroidism are real but nonspecific. Each one has many other possible causes, so no single symptom can identify the condition (Jansen et al., 2023). A 2021 review in American Family Physician lists cold intolerance, fatigue, weight gain, dry skin, constipation, and voice changes among the more common symptoms (Wilson et al., 2021). The table below sets those beside signs that tend to get less attention.
| More common symptoms | Less recognized signs |
|---|---|
| Fatigue | Thinning of the outer eyebrows |
| Weight gain | Dry, thinning, or falling hair |
| Cold intolerance | Muscle aches, cramps, and joint pain |
| Dry skin | Puffiness around the eyes |
| Constipation | Heavier menstrual periods |
| Voice changes, including hoarseness | Slow heart rate |
Hypothyroid fatigue and weight gain
Fatigue and weight gain are two of the more common hypothyroid symptoms (Wilson et al., 2021). Both are nonspecific, and either can result from many factors other than a shortage of thyroid hormone (Jansen et al., 2023). That makes them easy to misread.
The thyroid's effect on weight is smaller than many people expect. Hypothyroidism lowers resting energy expenditure, yet only a modest weight gain is linked to it, mostly through changes in body composition, and treating hypothyroidism typically produces a modest weight loss of less than 10% (Biondi, 2023). The relationship also runs the other way. People with obesity tend to have higher TSH levels, and that rise can come back down after weight loss from a lower-calorie diet or bariatric surgery (Biondi, 2023). A slightly raised TSH in someone carrying extra weight does not automatically mean undiagnosed hypothyroidism, and it is not automatically the cause of the weight.
Thyroid hormone is not a weight-loss treatment either. Guidelines from the European Society of Endocrinology and the American Thyroid Association say that people with obesity whose only finding is a raised TSH with normal free T4 should not be treated with levothyroxine to lose weight (Biondi, 2023).
Less obvious signs that are easy to overlook
Muscle aches, cramps, and joint pain are easy to file under overwork, aging, or early arthritis, yet all of them appear on the symptom list for hypothyroidism (Wilson et al., 2021). When each complaint gets its own explanation, nobody connects them.
Hair thinning is another easily missed sign. Thinning at the outer edges of the eyebrows is a recognized clinical finding, and scalp hair can become dry, thin, or start to fall out (Wilson et al., 2021). Memory problems and trouble concentrating are on the symptom list too.
A 2023 review in Frontiers in Endocrinology adds an important caveat. Many people with subclinical hypothyroidism have no symptoms at all, and in a large population study, people with subclinical hypothyroidism reported thyroid-type symptoms at rates similar to people with normal thyroid function (Jansen et al., 2023). Symptoms are a reason to test for undiagnosed hypothyroidism. They are not a diagnosis.
Can hypothyroidism go undetected for years?
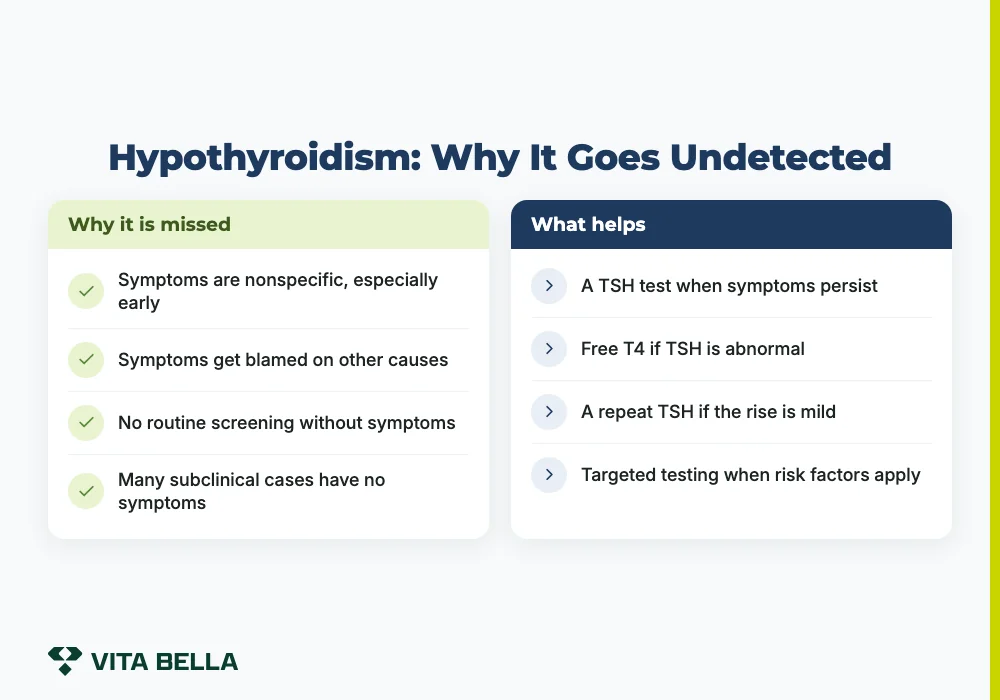
It can stay unrecognized for a long time. The 2022 review in Current Medical Research and Opinion found that limited knowledge of hypothyroidism, combined with the tendency to blame its symptoms on other causes, has led to substantial unawareness and often late diagnosis (Gottwald-Hostalek and Schulte, 2022). A 2019 meta-analysis of European studies estimated that 4.7% of the people studied had undiagnosed hypothyroidism, most of it subclinical (4.1%), and a sensitivity analysis suggested higher rates in women and in people aged 65 and older (Mendes et al., 2019).
Several things let undiagnosed hypothyroidism stay hidden:
- Nonspecific symptoms. Signs and symptoms are nondiagnostic, especially early on (Wilson et al., 2021), and they overlap with other conditions and with the effects of aging (Gottwald-Hostalek and Schulte, 2022).
- No routine screening. The U.S. Preventive Services Task Force found insufficient evidence to weigh the benefits and harms of screening nonpregnant adults who have no symptoms (Wilson et al., 2021).
- A subtle picture in older adults. Few older patients with confirmed hypothyroidism have obvious symptoms (Wilson et al., 2021).
Subclinical hypothyroidism, the most common form of undiagnosed hypothyroidism, is an elevated TSH with free T4 still in range, and it does not always progress. In data cited by the American Family Physician review, more than half of people older than 55 with a TSH of 5.0 to 9.9 mIU/L returned to normal without treatment, compared with 13% of those whose TSH was above 10 mIU/L. People with elevated thyroid peroxidase (TPO) antibodies are at higher risk of progressing to overt hypothyroidism (Wilson et al., 2021).
How long can hypothyroidism go undiagnosed?
How long undiagnosed hypothyroidism goes unrecognized varies from person to person. The 2022 review describes late diagnosis as common (Gottwald-Hostalek and Schulte, 2022), and in older adults the presentation can be subtle enough to escape notice (Wilson et al., 2021).
Some groups warrant a closer look. The American Family Physician review suggests considering targeted thyroid screening when one of the following is first diagnosed or started: type 1 diabetes, Addison disease, Down syndrome, Turner syndrome, partial thyroid removal, radioactive iodine treatment, radiation to the neck, or medications such as amiodarone, lithium, interferons, or rifampin (Wilson et al., 2021). If any of these apply to you and you have never had thyroid lab testing, raise it with your clinician.
Can hypothyroidism be misdiagnosed as depression?
It can be overlooked that way. Depression, fatigue, memory problems, and difficulty concentrating all appear on the symptom list for hypothyroidism (Wilson et al., 2021), and they overlap heavily with a depressive episode. People also tend to attribute hypothyroid symptoms to other causes (Gottwald-Hostalek and Schulte, 2022), so an underactive thyroid can be missed if low mood is put down to depression alone. That overlap is where the risk of hypothyroidism misdiagnosis comes from.
A TSH test is the first step in checking for undiagnosed hypothyroidism. A normal result makes primary hypothyroidism unlikely, while a high result needs a free T4 test to confirm and classify it (Wilson et al., 2021). When TSH is normal but symptoms persist, depression and anxiety are among the conditions the American Family Physician review lists for clinicians to consider instead.
The two can also coexist. A meta-analysis cited in the same review found an excess risk of depression in people with subclinical hypothyroidism but no improvement with levothyroxine (Wilson et al., 2021), and the trials behind a 2019 BMJ guideline showed no clinically relevant benefit of thyroid hormones for depressive symptoms or fatigue (Bekkering et al., 2019). The review notes one possible exception: people with treatment-resistant depression and a TSH above 2.5 mIU/L may benefit from thyroid hormone therapy (Wilson et al., 2021). Otherwise, a mildly raised TSH should not be assumed to explain low mood. Depression deserves its own assessment and care.
Hashimoto thyroiditis, an autoimmune condition, is the most common cause of hypothyroidism in the United States (Wilson et al., 2021). Hashimoto thyroiditis symptoms are largely the symptoms of hypothyroidism itself, since the condition is a form of primary thyroid failure. A TPO antibody test does not diagnose hypothyroidism. A positive result does suggest an autoimmune cause, and in someone with subclinical hypothyroidism, elevated TPO antibodies signal a higher risk of progressing to overt disease (Wilson et al., 2021).
What TSH level indicates hypothyroidism?
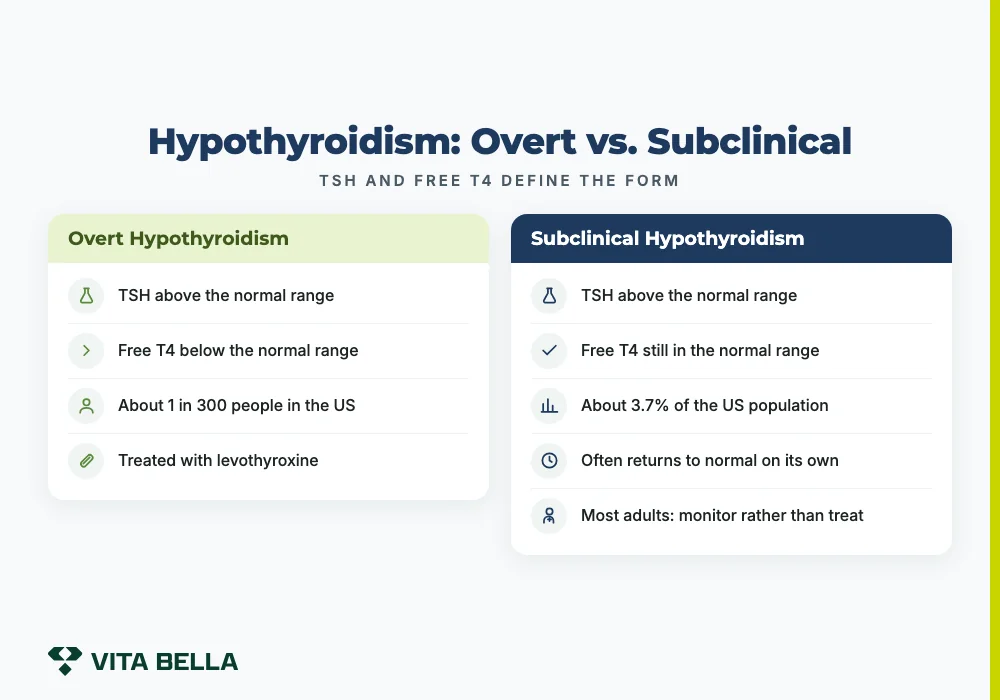
In primary hypothyroidism, the common type, an elevated TSH is the key finding. The American Family Physician review gives a normal TSH range of about 0.4 mIU/L at the low end to 4.0 to 4.5 mIU/L at the upper end, and it recommends checking free T4 when TSH is above 4.5 mIU/L (Wilson et al., 2021). In the rare central forms, which start in the pituitary or hypothalamus, TSH can be normal or low. Free T4 then defines the form:
- Overt (clinical) hypothyroidism: high TSH with low free T4. Guidelines advise treating it whether or not symptoms are present (Jansen et al., 2023).
- Subclinical hypothyroidism: high TSH with free T4 still in the normal range.
Clinical hypothyroidism affects about 1 in 300 people in the United States. The subclinical form is far more common, at about 3.7% of the population (Wilson et al., 2021).
Reference ranges are not one-size-fits-all. TSH tends to rise with age, and a mild elevation in an older adult does not necessarily mean subclinical hypothyroidism (Wilson et al., 2021). Applying the same TSH range across the whole adult lifespan makes the diagnosis more likely in older people (Holley et al., 2024). Ranges also differ between laboratories and test methods, so results are best read against the range printed on your own report (Jansen et al., 2023). Our guide to how lab reference ranges are built explains where these ranges come from.
A single mild result often normalizes. After a first subclinical finding, the American Family Physician review recommends a TPO antibody test and a repeat TSH in 6 to 12 months (Wilson et al., 2021), while a 2023 review suggests repeating TSH after 2 to 3 months to rule out a temporary rise (Jansen et al., 2023).
Subclinical hypothyroidism symptoms and the treatment question
Subclinical hypothyroidism symptoms vary. Many people have none, others report milder versions of overt symptoms, and studies disagree on whether mood, memory, or quality of life are affected (Jansen et al., 2023).
The treatment evidence is clearer. A 2018 JAMA meta-analysis of 21 randomized trials with 2,192 adults found that thyroid hormone therapy brought TSH into the normal range but was not associated with better quality of life or fewer thyroid-related symptoms than placebo or no treatment (Feller et al., 2018). Building on that evidence, a 2019 BMJ clinical practice guideline made a strong recommendation against thyroid hormones for adults with subclinical hypothyroidism (Bekkering et al., 2019). It does not apply to women trying to become pregnant or to people with TSH above 20 mIU/L, and it may not apply to young adults (about 30 or younger) or people with severe symptoms. For everyone else, the panel advises monitoring whether the thyroid dysfunction progresses or resolves. The American Family Physician review adds that most adults older than 30 with this pattern do not benefit from thyroid hormone therapy, and that 60% return to normal within five years (Wilson et al., 2021).
Not every guideline goes that far. The American and European thyroid associations advise treatment when TSH is 10 mIU/L or higher, or when a TSH of 4 to 4.5 mIU/L or above comes with symptoms or other conditions, taking age into account (Jansen et al., 2023). The American Family Physician review recommends considering levothyroxine for nonpregnant adults with subclinical hypothyroidism only when TSH is above 10 mIU/L or TPO antibodies are elevated, and it cites a study linking levothyroxine to higher mortality in people 65 and older with subclinical hypothyroidism and a TSH below 10 mIU/L (Wilson et al., 2021). Weighing these options is a job for a licensed provider who can look at labs, antibodies, age, symptoms, and pregnancy plans together.
Untreated hypothyroidism effects: what the evidence shows
Untreated hypothyroidism effects depend on which form is present. Because most undiagnosed hypothyroidism is subclinical (Mendes et al., 2019), the second group below is the larger one.
Overt hypothyroidism that goes untreated can contribute to numerous physiologic and metabolic problems (Wilson et al., 2021). Findings associated with it include higher LDL cholesterol and triglycerides, anemia, a slow heart rate, diastolic high blood pressure, and fluid retention. At the severe end, myxedema coma is a rare medical emergency, most often seen in older adults with primary hypothyroidism, and it needs urgent treatment. In pregnancy, untreated hypothyroidism can lead to miscarriage, preeclampsia, preterm birth, placental abruption, and fetal death (Wilson et al., 2021).
Subclinical hypothyroidism is a different story. In older adults, it has been associated with depression, cognitive impairment, high blood lipids, and coronary artery disease, yet there is no evidence that treating it improves those outcomes (Wilson et al., 2021). The same review calls the benefit of treatment uncertain in many other groups. People with a TSH above 10 mIU/L had a higher risk of fracture, ischemic heart disease, and heart failure than people with a TSH of 2.0 to 2.5 mIU/L (Wilson et al., 2021).
A 2024 meta-analysis of adults over 65 with subclinical hypothyroidism found no significant difference in cardiovascular risk between those treated with levothyroxine and those left untreated (Holley et al., 2024). A 2023 review in Nutrients notes that subclinical hypothyroidism and metabolic syndrome are each associated with atherosclerosis and with liver and kidney disease, so having both may add to the risk. Its author favors identifying and treating subclinical hypothyroidism in people with obesity, but notes that randomized trials have yet to confirm that treatment offsets these risks, and that a TSH raised by excess weight alone can fall with weight loss (Biondi, 2023).
Fertility and pregnancy deserve separate attention. Subclinical hypothyroidism in pregnancy is associated with adverse outcomes such as miscarriage, preterm delivery, and low birth weight, but treatment trials have been mixed, and the benefit of treating women who are pregnant or trying to conceive is unclear (Wilson et al., 2021). People with a TSH above 2.5 mIU/L and positive TPO antibodies have a higher risk of pregnancy complications such as preterm birth and pregnancy loss (Wilson et al., 2021). A 2024 American Society for Reproductive Medicine guideline describes treating subclinical hypothyroidism in women with infertility as controversial and reviews its risks and benefits (Practice Committee of the ASRM, 2024). Women trying to conceive should review thyroid results with a clinician; the BMJ recommendation against thyroid hormones does not apply to them (Bekkering et al., 2019).
Getting tested: a practical path forward
Finding undiagnosed hypothyroidism starts with one blood test. When symptoms raise suspicion, clinicians order TSH first, and if it is abnormal, free T4 follows to confirm and classify the result (Wilson et al., 2021). Choosing Wisely recommendations cited in the same review advise against ordering multiple thyroid tests at the first visit, and routinely measuring total T3, total T4, or free T3 is not indicated. Once TSH is high, a positive TPO antibody test suggests an autoimmune cause.
Thyroid lab testing makes the most sense when symptoms persist without a clear cause or when one of the risk factors listed above applies. If you are already working with a provider on testosterone or another hormone, mention thyroid-type symptoms as well. Fatigue, low energy, trouble concentrating, and weight changes have many possible causes besides the thyroid, from anemia and sleep apnea to menopause and depression (Wilson et al., 2021). Testing narrows the list.
For people who are already diagnosed and treated but still feel unwell, the American Family Physician review advises reassessing for other causes or referral when symptoms persist despite adequate treatment. It advises against T3, alone or added to levothyroxine, and notes that the American Thyroid Association does not recommend genetic testing to guide treatment, although a small subset of patients with a specific gene variant may benefit from combination therapy (Wilson et al., 2021). Our article on thyroid hormone fine-tuning looks at persistent symptoms in more detail.
Severe iodine deficiency, the most common cause of hypothyroidism in many parts of the world, rarely causes it in the United States because of iodized salt, and the review advises against iodine supplements, including kelp, where iodine intake is sufficient (Wilson et al., 2021).
Could your thyroid be behind your symptoms?
If fatigue, weight changes, low mood, hair thinning, or cold intolerance have lasted without a clear cause, a TSH test to check for undiagnosed hypothyroidism is a reasonable next step to discuss with a clinician. Vita Bella providers can include thyroid testing in a broader hormone evaluation when symptoms call for it, so overlapping causes are looked at together. Get Started
Frequently asked questions
It can stay unrecognized for a long time. Its symptoms are nonspecific, especially early on, and people often attribute them to other causes, which leads to late diagnosis. Because population screening has not been shown to be beneficial, the search for undiagnosed hypothyroidism focuses on people with symptoms or risk factors.
More common signs include fatigue, weight gain, cold intolerance, dry skin, constipation, and voice changes. Less recognized ones include thinning of the outer eyebrows, hair changes, muscle aches and cramps, puffiness around the eyes, heavier periods, and a slow heart rate. None of these is specific to the thyroid, so blood tests, not the symptom list, are how undiagnosed hypothyroidism is confirmed: TSH first, then free T4 if TSH is abnormal.
It can be overlooked that way, because low mood, fatigue, memory problems, and poor concentration occur in both conditions. A TSH test shows whether thyroid dysfunction is present, but the two can coexist: subclinical hypothyroidism carries an excess risk of depression, and levothyroxine has not been shown to improve it, so mood symptoms still need their own assessment.
A TSH above the normal range, which tops out at about 4.0 to 4.5 mIU/L, is considered elevated, although ranges differ between laboratories. With low free T4, it indicates overt hypothyroidism, which guidelines advise treating. With normal free T4, it indicates subclinical hypothyroidism; because mild elevations often return to normal, the American Family Physician review recommends a TPO antibody test and a repeat TSH in 6 to 12 months.
Untreated overt hypothyroidism is associated with higher LDL cholesterol and triglycerides, a slow heart rate, and, in pregnancy, a higher risk of miscarriage, preeclampsia, and preterm birth. In rare severe cases it can lead to myxedema coma, a medical emergency. Mild subclinical hypothyroidism is different: it often returns to normal on its own, treatment has not been shown to improve quality of life or symptoms in most adults, and in adults over 65 treatment was not linked to a significant difference in cardiovascular risk. Monitoring is the usual approach, with treatment considered mainly when TSH is above 10 mIU/L or TPO antibodies are elevated.
Sources
- Mendes D, Alves C, Silverio N, Batel Marques F (2019). Prevalence of Undiagnosed Hypothyroidism in Europe: A Systematic Review and Meta-Analysis. European Thyroid Journal. PubMed
- Gottwald-Hostalek U, Schulte B (2022). Low awareness and under-diagnosis of hypothyroidism. Current Medical Research and Opinion. PubMed
- Wilson SA, Stem LA, Bruehlman RD (2021). Hypothyroidism: Diagnosis and Treatment. American Family Physician. PubMed
- Feller M et al. (2018). Association of Thyroid Hormone Therapy With Quality of Life and Thyroid-Related Symptoms in Patients With Subclinical Hypothyroidism: A Systematic Review and Meta-analysis. JAMA. PubMed
- Bekkering GE et al. (2019). Thyroid hormones treatment for subclinical hypothyroidism: a clinical practice guideline. BMJ. PubMed
- Practice Committee of the American Society for Reproductive Medicine (2024). Subclinical hypothyroidism in the infertile female population: a guideline. Fertility and Sterility. PubMed
- Holley M et al. (2024). Cardiovascular and bone health outcomes in older people with subclinical hypothyroidism treated with levothyroxine: a systematic review and meta-analysis. Systematic Reviews. PubMed
- Biondi B (2023). Subclinical Hypothyroidism in Patients with Obesity and Metabolic Syndrome: A Narrative Review. Nutrients. PubMed
- Jansen HI et al. (2023). Hypothyroidism: The difficulty in attributing symptoms to their underlying cause. Frontiers in Endocrinology. PubMed
















