



Testosterone to estrogen conversion happens in every man. It is not a side effect to suppress. The enzyme aromatase converts a portion of circulating testosterone into estradiol through a process called aromatization, and on testosterone replacement therapy that conversion rate typically increases because more substrate is available. Estradiol in appropriate amounts supports bone density, sexual function, and cardiovascular health. Problems emerge at both extremes: levels that run too high, and levels driven too low by over-aggressive management.
Does testosterone convert to estrogen in men?
Yes, continuously. Testosterone to estrogen conversion runs throughout a man's life through the activity of aromatase (CYP19A1), an enzyme that transforms testosterone into estradiol through three successive hydroxylation reactions. All men experience this. On TRT, the rate increases.
The testes directly secrete roughly 20% of a man's circulating estradiol. The remaining 80% comes from peripheral conversion in adipose tissue, skeletal muscle, bone, and brain. Daily estradiol production in adult men averages around 35 to 45 micrograms.
Circulating estradiol runs at roughly 1/200th the concentration of testosterone. Low in absolute terms, but biologically active throughout multiple systems. Men carry estrogen receptors in the skeleton, vascular tissue, brain, and reproductive organs. A 2023 review in Endotext by Rochira et al. documents how estradiol regulates gonadotropin feedback, bone remodeling, fat distribution, and aspects of sexual response in men.
Aromatization in men occurs primarily at these peripheral sites:
- Adipose tissue converts the largest share, and the rate increases with higher body fat percentage.
- Skeletal muscle accounts for a meaningful portion of peripheral conversion throughout the body.
- Bone tissue converts testosterone locally, directly influencing the regulation of bone-forming and bone-resorbing cells.
- The brain and hypothalamus convert testosterone to estradiol to support mood, cognitive function, and hormonal feedback.
- The testes secrete approximately 20% of circulating estradiol directly, independent of peripheral aromatization.
On TRT, exogenous testosterone raises the total androgen load available to all of these sites. More substrate means more conversion, which is why estradiol monitoring belongs in any well-designed protocol from the start.
What is a normal estradiol level for men on TRT?
The commonly cited male estradiol reference range runs from about 10 to 40 pg/mL. Estradiol levels on TRT often sit toward the upper portion or modestly beyond that range, because more testosterone substrate is available for aromatization. Whether a given reading is a problem depends far more on symptoms than on the number alone.
Understanding what optimal estradiol looks like beyond a standard reference range matters here. Two men can show identical estradiol readings with opposite symptom pictures, based on their testosterone level, SHBG concentration, and individual receptor sensitivity. A reading at the high end of the population reference range with no matching symptoms is typically not a problem requiring intervention.
A 2018 Endocrine Society Clinical Practice Guideline by Bhasin et al. advises monitoring estradiol during TRT and basing any management on clinical findings. The guideline does not endorse routine estradiol suppression as a default component of TRT.
Providers evaluate the estradiol result within the full clinical picture. The number alone is not enough. Where testosterone sits, how the man feels, and whether symptoms pointing specifically to estradiol excess are present all determine whether management is warranted.
Why estradiol matters in men on TRT
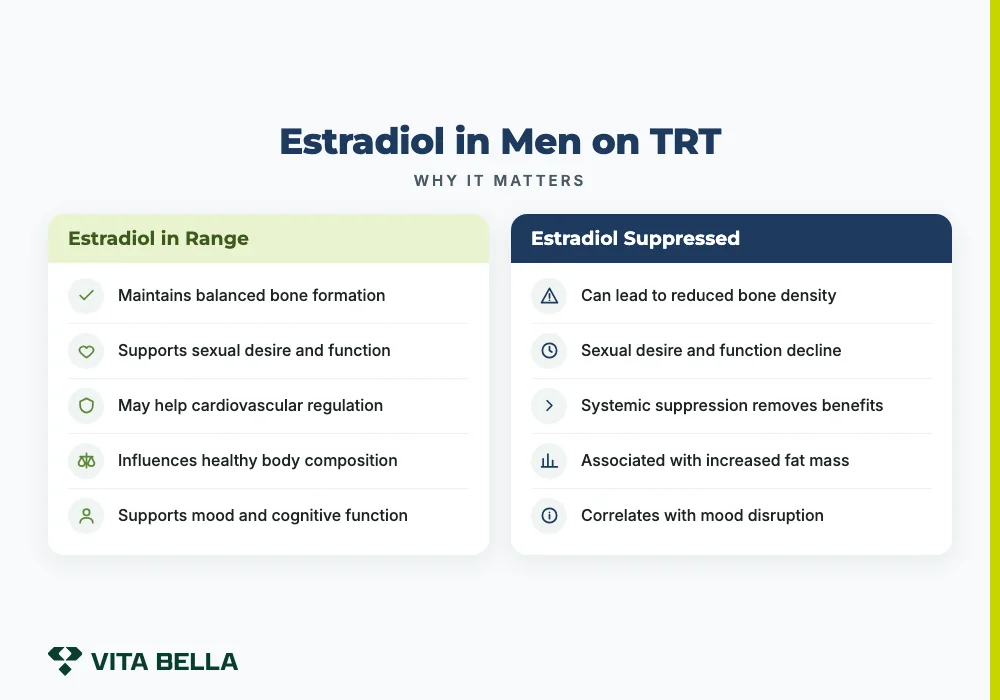
The estradiol role in male health extends well beyond reproduction, it functions as an active hormone across multiple systems in men. When testosterone to estrogen conversion keeps levels in range, several systems depend on it:
- Bone remodeling requires estradiol to limit excessive osteoclast activity and maintain balanced bone formation throughout the skeleton.
- Sexual desire and erectile function both decline measurably when estradiol is suppressed, as direct clinical trial evidence demonstrates.
- Local aromatization in vascular and cardiac tissue may contribute to cardiovascular regulation in ways that systemic suppression removes.
- Fat distribution and body composition respond to estradiol status in men, with suppression associated with increased fat mass.
- Mood and cognitive function rely on estrogen receptor activation in the brain, and low estradiol correlates with mood disruption independent of testosterone level.
These are not peripheral effects. Research in men with genetic aromatase deficiency and clinical trials that directly manipulate estradiol levels confirm that the hormone performs essential work. The goal on TRT is to maintain it, not to minimize it.
Bone density estradiol men: what the evidence shows
Men born with complete aromatase deficiency cannot perform any testosterone to estrogen conversion. Despite normal or elevated testosterone, they develop significantly reduced bone mineral density, failed epiphyseal closure, and elevated bone turnover markers. Estradiol replacement corrects these findings. Testosterone alone does not. That isolates estradiol's skeletal contribution directly.
A 2015 analysis by Cauley in Steroids found that lower bioavailable estradiol in aging men predicts faster bone loss and higher fracture risk, independently of testosterone. A 2021 narrative review by Shigehara et al. in Journal of Clinical Medicine confirmed that TRT raises bone mineral density in hypogonadal men, with aromatization to estradiol identified as a contributing pathway.
A 2024 evidence synthesis by Cruickshank et al. in Health Technology Assessment reviewed TRT outcomes across multiple endpoints in hypogonadal men, including bone mineral density, confirming skeletal benefit as a documented effect of testosterone therapy.
A 2025 study by Yao et al. in Medicinal Research Reviews extends the bone picture through immunology. Estrogen deficiency disrupts the balance of immune cells that govern bone remodeling, increasing osteoclast-promoting signals and reducing opposing ones. That immune-mediated mechanism is not exclusive to postmenopausal women.
Any man with chronically suppressed estradiol faces the same shift in bone biology.
Sexual function and the estradiol connection
The 2013 trial by Finkelstein et al. in the New England Journal of Medicine directly assigned men to different combinations of testosterone and estradiol suppression to separate their contributions. Sexual desire and erectile capacity dropped most sharply when both hormones were suppressed together. When testosterone was maintained but estradiol was blocked, sexual function still declined significantly.
That trial established that estradiol contributes to male sexual function independently of testosterone, not as a secondary byproduct.
Cardiovascular effects of testosterone to estrogen conversion
Research by Gersh et al. in Progress in Cardiovascular Diseases (2024) documents estradiol's role in lipid regulation, inflammatory response, and vascular tone. A 2023 paper by Eissa et al. in Biomedicine and Pharmacotherapy reviewed aromatase activity in cardiac and renal tissue and found that local testosterone to estrogen conversion at those sites may contribute to cardioprotective effects associated with adequate estradiol levels.
Blocking aromatase systemically to manage circulating estradiol also removes this local conversion from tissues where it may support cardiovascular function.
What happens if estrogen is too low on testosterone therapy?
When estradiol drops too low on TRT, a distinct symptom pattern develops. It is often missed because it overlaps with symptoms TRT is supposed to address.
Possible signs that estradiol may be too low include:
- Joint pain and stiffness may develop, particularly in the knees, hips, and wrists, with no mechanical cause.
- Sexual desire may decline even when testosterone levels are within range.
- Erections may become difficult to achieve or maintain despite adequate testosterone.
- Mood may shift toward irritability, low motivation, or persistent emotional flatness.
- Fatigue and poor sleep quality may persist despite otherwise appropriate hormone levels.
- Skin may become dry and thin, losing elasticity over time.
These symptoms can look identical to undertreated low testosterone. Labs are the only reliable way to distinguish the two. A man reporting that TRT is not working may be experiencing over-suppressed estradiol rather than any problem with testosterone.
A 2011 review by de Ronde and de Jong in Reproductive Biology and Endocrinology examining aromatase inhibitor use in men identified sexual function impairment and skeletal effects as the most clinically consistent problems associated with estradiol suppression. Those findings align directly with aromatase-deficient male physiology.
High estradiol symptoms TRT patients describe
High estradiol symptoms TRT patients report most often differ from the low-estradiol picture but share some overlap. Possible effects include:
- Breast tissue tenderness or sensitivity may appear, and may progress to gynecomastia if estradiol remains persistently elevated.
- Water retention and bloating may occur, typically most noticeable in the abdomen and face.
- Mood may shift toward emotional sensitivity or increased anxiety, distinct from the flat affect of low estradiol.
- Libido may decline in some men at elevated estradiol levels.
- Fatigue and reduced energy may persist despite testosterone being in range.
The overlap between high and low estradiol symptom profiles is real and clinically significant. Symptoms alone cannot identify which direction the problem lies. Only lab testing provides that clarity, which is why estradiol monitoring during TRT is standard clinical practice rather than optional follow-up.
How do aromatase inhibitors affect testosterone replacement therapy?
Aromatase inhibitors block testosterone to estrogen conversion by inhibiting the CYP19A1 enzyme throughout the body, reducing circulating estradiol. Anastrozole is the AI most commonly prescribed alongside TRT.
Used selectively when labs confirm elevated estradiol alongside clear matching symptoms, such as breast tissue sensitivity or significant fluid retention, an AI can address those effects. A licensed provider determines the dose after reviewing labs and symptoms together. That is the appropriate clinical role for these medications.
Anastrozole TRT risks become a concern when AIs are prescribed as a default component of every protocol, regardless of whether estradiol is elevated or causing symptoms. That approach often drives estradiol below the range that supports bone health, libido, and joint function.
The 2018 Endocrine Society guideline by Bhasin et al. does not recommend routine AI co-prescription with TRT.
Aromatase inhibitor side effects that emerge with over-suppression include the low-estradiol symptom set: joint stiffness, loss of sexual desire despite adequate testosterone, mood disruption, and progressive bone density reduction with chronic use. A man who starts an AI to manage one symptom can inadvertently acquire several others.
Not every man on TRT requires AI management. Some convert slowly and maintain comfortable estradiol without intervention. Others benefit from careful, symptom-directed use at a dose the provider selects after reviewing labs. The management approach follows the clinical picture, not a standing protocol.
Can high body fat increase estrogen conversion on TRT?
Yes. Adipose tissue is the main site of peripheral testosterone to estrogen conversion in men. Fat cells express aromatase in significant amounts, and more adipose tissue means more conversion capacity. Two men on identical TRT protocols can arrive at substantially different estradiol readings based on body fat percentage alone.
Providers account for body composition when reviewing estradiol results. A reading that appears elevated in isolation may reflect adipose-driven aromatization rather than any protocol problem. Context determines what a number means.
Reducing body fat through training and nutrition can modestly lower the aromatization rate over time. Nutritional factors interact with androgen status as well. A 2023 paper by Whittaker in Nutrition and Health examined dietary influences on testosterone regulation, noting that overall nutritional status shapes the androgen environment in ways that intersect with conversion rate. These are long-arc changes, and regular lab monitoring remains the practical tracking tool during the process.
Aromatization rate also increases with age as body composition shifts toward more fat and less lean mass. That is one reason estradiol management on TRT is not a one-time calibration but part of ongoing quarterly provider oversight.
Managing testosterone to estrogen conversion: what providers track
A well-run protocol treats estradiol as part of a clinical picture, not a fixed number to suppress by default. Providers review estradiol alongside testosterone levels, how SHBG influences free testosterone and estradiol availability, symptom tracking, and body composition.
The lab markers your provider reviews before and during TRT typically include baseline estradiol, total and free testosterone, SHBG, complete blood count, and metabolic markers. These results shape both the starting protocol and the monitoring frequency.
Labs before TRT begins establish the baseline. Regular monitoring catches changes as the protocol develops.
Several individual factors shape how testosterone to estrogen conversion plays out for any given man:
- Higher body fat percentage increases aromatization rate most consistently across the research.
- Older age tends to increase aromatase activity as lean mass decreases over time.
- Higher testosterone levels produce more substrate, leading to more conversion overall.
- More frequent, smaller-dose injections tend to produce more stable estradiol levels than large infrequent doses.
- Genetic differences in CYP19A1 expression create meaningful variation in aromatization rate between men.
- Zinc status modestly influences aromatase activity, with deficiency associated with slightly higher conversion.
No single factor is determinative. Two men with similar body composition can respond differently based on genetics alone. Providers at Vita Bella build quarterly check-ins around both lab results and symptom tracking, which is how small estradiol shifts get caught before they compound into larger problems.
Ready to start your protocol?
Get Started with a provider who reviews your full labs before and during TRT, assessing estradiol alongside testosterone for a complete clinical picture.
Frequently asked questions
Not always to a degree requiring management, but estradiol typically rises when testosterone is added because more substrate becomes available for aromatization. How much it rises depends on body fat, genetics, dose, and injection frequency, which is why monitoring estradiol is standard TRT care.
There is no universal threshold. Concern typically arises when estradiol exceeds the standard male reference range together with matching symptoms such as breast tissue tenderness, significant water retention, or mood changes. A provider interprets the reading within the full symptom and hormone picture.
A provider requires lab results before prescribing an AI because high and low estradiol produce overlapping symptoms. Using an AI without confirmed elevated estradiol risks driving levels too low and replacing one set of problems with another, including joint pain, libido loss, and bone effects over time.
Symptoms may develop within weeks if estradiol rises quickly. For some men, the rise is gradual and effects build over months. Standard practice is to check labs at roughly 6 to 8 weeks after starting or adjusting a protocol, which captures changes before they become pronounced.
Prolonged estradiol suppression increases bone turnover and reduces bone mineral density over time. Research in aromatase-deficient men and clinical studies of aromatase inhibitor use in men consistently show that adequate estradiol, not testosterone alone, is required for skeletal maintenance.
Sources
- Rochira V, et al. (2023). Estrogens, male reproduction and beyond. In: Endotext. MDText.com. PubMed
- Bhasin S, et al. (2018). Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline. The Journal of Clinical Endocrinology and Metabolism. PubMed
- Cauley JA. (2015). Estrogen and bone health in men and women. Steroids. doi:10.1016/j.steroids.2014.12.010.
- Shigehara K, et al. (2021). Testosterone and bone health in men: a narrative review. Journal of Clinical Medicine. doi:10.3390/jcm10030530.
- Finkelstein JS, et al. (2013). Gonadal steroids and body composition, strength, and sexual function in men. New England Journal of Medicine. doi:10.1056/NEJMoa1206168.
- de Ronde W, de Jong FH. (2011). Aromatase inhibitors in men: effects and therapeutic options. Reproductive Biology and Endocrinology. doi:10.1186/1477-7827-9-93.
- Yao Y, et al. (2025). Estrogen deficiency-mediated osteoimmunity in postmenopausal osteoporosis. Medicinal Research Reviews. PubMed
- Gersh F, et al. (2024). Estrogen and cardiovascular disease. Progress in Cardiovascular Diseases. PubMed
- Eissa MA, et al. (2023). Aromatase enzyme: Paving the way for exploring aromatization for cardio-renal protection. Biomedicine and Pharmacotherapy. PubMed
- Whittaker J. (2023). High-protein diets and testosterone. Nutrition and Health. PubMed
- Cruickshank M, et al. (2024). The effects and safety of testosterone replacement therapy for men with hypogonadism. Health Technology Assessment. PubMed
















